
Health
Extreme Heat Threatens Pregnancies, Exposing Gaps in Climate Adaptation Plans
Extreme heat is emerging as a growing threat to pregnancy and childbirth. Research from India and an international survey highlight the risks to maternal and newborn health, underscoring the need for stronger healthcare protections and climate adaptation plans.


Evidence from Tamil Nadu and a new international survey shows how rising temperatures threaten maternal and newborn health, with outdoor workers and rural women facing particular risks.
Extreme heat is emerging as a growing threat to pregnancy and childbirth, but climate adaptation plans risk overlooking the women and newborns most vulnerable to its effects. New international survey findings, alongside research from Tamil Nadu, point to a widening public-health challenge as rising temperatures threaten maternal health and expose inequalities in access to safe healthcare.
At least 73% of maternal healthcare professionals surveyed across five countries reported an increase in heat-related cases or complications affecting pregnant women over the past five years, according to a survey commissioned by global charitable foundation Wellcome. Meanwhile, 76% reported an increase in heat-related complications affecting foetal or newborn health.
The findings were highlighted by Simon Stiell, executive secretary of the United Nations Framework Convention on Climate Change (UNFCCC), at an event organised by Wellcome during the Pre-COP ministerial meeting in Fiji on October 5, ahead of the COP31 climate conference in Türkiye in November.
“Rising temperatures mean rising danger in pregnancy,” Stiell said, pointing to links between extreme heat during pregnancy and premature birth, stillbirth, low birth weight and maternal complications.
The survey covered 1,000 maternal healthcare professionals working in Australia, Brazil, India, the United Kingdom and Zimbabwe. It found that 81% were concerned that extreme heat would increasingly threaten maternal, foetal and newborn health without further action. Nearly all respondents had cared for a pregnant woman or baby whose health they believed had been affected by extreme heat, while 92% wanted more training and resources to protect pregnant women.
The findings highlight a critical gap in climate preparedness: although heat-health warnings are becoming increasingly important, pregnancy and newborn care are not always adequately incorporated into plans for responding to extreme temperatures.
Evidence from India highlights unequal risks
Research from Tamil Nadu adds to the growing evidence that occupational heat exposure can have serious consequences for pregnancy.
A prospective cohort study published in BJOG: An International Journal of Obstetrics & Gynaecology examined 800 pregnant women engaged in moderate to heavy physical work in Tamil Nadu. Researchers found that 47.3% experienced high occupational heat exposure. Among heat-exposed women, 29.6% experienced moderate dehydration, while 17.4% recorded an increase in core body temperature.
The study found that women exposed to high occupational heat had 2.4 times the adjusted odds of miscarriage and 2.3 times the adjusted odds of an adverse pregnancy outcome. The latter included outcomes such as miscarriage, preterm birth, low birth weight and stillbirth.

Children are attending school in temporary learning centres following the devastating floods in Nuwakot, Nepal, where climate change and glacial ice melt have played a significant factor.Image credit: UNICEF/Laxmi Prasad Ngakhusi
The researchers also found that high occupational heat exposure was associated with twice the adjusted odds of an adverse outcome at birth. Although the study establishes an association rather than proving that heat alone caused each outcome, it provides evidence of the risks faced by pregnant women working in hot conditions.
A separate observational cohort study involving 680 pregnant women across six Tamil Nadu districts examined differences between rural and urban populations. Researchers found that 55% of rural participants experienced heat exposure above the study’s permissible limit, compared with 45% of urban participants.
Rural women were also more likely to report heat-strain symptoms, including excessive thirst, fatigue, headaches and dizziness. After accounting for potential confounding factors, heat-exposed rural women had nearly twice the risk of adverse pregnancy outcomes and three times the risk of adverse birth outcomes compared with the study’s urban comparison group.
The study also found a fourfold higher risk of miscarriage among heat-exposed rural women during the first trimester compared with urban women. The researchers identified socioeconomic disadvantage, limited awareness of heat risks and reduced access to welfare facilities as factors that could contribute to rural women’s greater vulnerability.
Evidence from a separate study of 126,273 pregnancies recorded in India and Pakistan reinforces the concern. Researchers found that higher average maximum temperatures during the second trimester were associated with an increased risk of preterm birth. The relative risk was 1.05 for the study’s five-degree temperature contrast, indicating a 5% relative increase in risk—not a five-percentage-point increase in the absolute risk of premature birth.
Together, these studies suggest that heat exposure is not simply an environmental inconvenience during pregnancy. It can coincide with dehydration, physically demanding work and barriers to healthcare, creating risks that are unevenly distributed across communities.
From warnings to protection
Stiell warned that the effects of extreme heat are not shared equally. Pregnant women who work outdoors, live in poorly ventilated housing, travel long distances to clinics or depend on healthcare facilities without reliable electricity, water or cooling cannot be protected through public advice alone.
“Staying cool” is not a realistic option for families without access to cool spaces, he argued. Without targeted intervention, extreme heat could deepen existing inequalities in maternal healthcare, making a safe pregnancy increasingly dependent on income, geography and access to medical services.
Stiell outlined three priorities for governments: integrating pregnancy and newborn care into climate adaptation and heat-health planning; translating evidence into practical protection through healthcare-worker training, heat alerts and safer facilities; and improving data to identify where risks are growing and which interventions are effective.
For India, the findings have implications for heat-action plans, occupational safety and maternal healthcare. Measures could include heat-risk guidance during antenatal visits, better protection for pregnant outdoor workers, improved ventilation and cooling in maternity facilities, and reliable access to water and electricity during extreme heat.
The UN climate chief also called for adaptation-finance commitments agreed at COP30 in Belém, Brazil, to be delivered and for countries to work towards mobilising $1.3 trillion annually for developing countries.
Health is expected to remain a key priority in preparations for COP31, scheduled for November 9–20, 2026, in Türkiye’s Antalya province, under the Turkish presidency and with Australia leading negotiations.
The emerging evidence makes the policy challenge clear: protecting pregnant women and newborns must become part of climate resilience, rather than an afterthought. As temperatures rise, governments will need to assess climate action not only by emissions targets and financial commitments, but also by whether healthcare systems can protect people during pregnancy and give newborns a safe start to life.






Health
Six months on, Ebola outbreak in DR Congo remains uncontrolled, with over 5,500 deaths
Six months after its declaration, the Ebola outbreak in DR Congo remains uncontrolled, with over 5,500 deaths. Armed conflict, gaps in disease surveillance and limited healthcare access continue to hamper containment efforts as the Bundibugyo virus spreads across eight provinces.

Six months after the Democratic Republic of the Congo (DRC) declared an Ebola outbreak, the disease remains out of control, with more than 11,300 confirmed cases and 5,500 deaths reported in the country. Despite an expanded international response, the outbreak continues to spread amid armed conflict, displacement and weaknesses in healthcare delivery.
The Africa Centres for Disease Control and Prevention (Africa CDC) warned on November 15 that the outbreak was still not under control. Its Director-General, Jean Kaseya, cautioned that unless transmission is interrupted, the epidemic could become the world’s worst Ebola outbreak.
According to the European Centre for Disease Prevention and Control (ECDC), the DRC had recorded 11,376 confirmed infections and 5,568 deaths as of November 15, based on data up to November 14. Eight provinces have been affected, with Ituri reporting the highest burden. The outbreak is caused by the Bundibugyo virus, a relatively rare species of Ebola virus.
Delayed detection is driving transmission
One of the biggest obstacles to containment is the inability to identify infected people and their contacts early. According to Africa CDC, more than 80% of new infections are being detected among people who were not previously listed as contacts of confirmed patients.
Contact tracing is central to Ebola control. Once an infection is confirmed, health workers identify people who may have been exposed and monitor them for symptoms during the 21-day incubation period. Failure to identify these contacts creates opportunities for further transmission.
More than 65% of deaths have occurred in communities rather than healthcare facilities, indicating that many patients are being identified too late to receive timely treatment. The World Health Organization (WHO) reported that children account for more than a quarter of confirmed infections and approximately one-third of deaths. Seven in 10 children under five who contract the disease have died.
The outbreak has expanded to 67 health zones across eight provinces, with an estimated 400–500 new cases being reported each week, according to the WHO’s November 14 update.
Conflict and insecurity disrupt response
Armed conflict and population displacement have further complicated containment. Insecurity has restricted access to affected communities, disrupted healthcare services and made surveillance and contact tracing difficult.
The WHO reported more than 80 attacks on healthcare since the outbreak began. An armed attack in Cantine-Aloya killed 66 civilians, including three health workers, while three healthcare facilities were looted. More than 1,000 contacts were subsequently lost to follow-up, and three confirmed patients could not be accounted for.
The response has also been affected by delayed payments to frontline health workers. Africa CDC has warned that inadequate resources, insufficiently trained personnel and operational difficulties are weakening efforts to contain the disease.

To help fight the spread of Ebola, UNICEF is supporting District Health Educators (DHE) in high-risk districts to conduct outreach activities with different groups, including corporate and business sectors, educational facilities, prisons, hostels and guest-houses. Photo: UNICEF/UNI790701/Bamulanzeki
Healthcare capacity expands, but gaps persist
There has been progress in strengthening the response. According to the WHO, diagnostic capacity has increased from two laboratories to more than two dozen, while nearly 2,000 treatment beds have been made available across 104 treatment and transit centres.
More than 17,000 community health workers and 46,000 community actors have received training to support surveillance, contact tracing and public awareness. Nearly 90% of registered deaths are now being managed through safe and dignified burials, reducing the risk of transmission during funerals.
However, these improvements have not translated into nationwide containment. Several initial outbreak centres, including Butembo, Mongbwalu and Nyankunde, have brought transmission under control, but new infections continue to emerge elsewhere.
The challenge of containing Bundibugyo virus
The virus itself presents another challenge. Bundibugyo is distinct from the Zaire ebolavirus responsible for the 2014–2016 West African epidemic. Vaccines developed against the Zaire species cannot be assumed to protect against Bundibugyo virus. There is currently no licensed vaccine specifically approved against this strain.
The international response therefore continues to depend on early diagnosis, isolation, supportive treatment, infection prevention and safe burial practices, alongside research into candidate vaccines and treatments.
The WHO has called for sustained, flexible funding through 2027 and improved access to communities affected by conflict. The outbreak has also prompted stronger cross-border surveillance, following infections reported in Kenya and Nigeria.
Six months into the crisis, the challenge is no longer simply mobilising an emergency response. It is ensuring that diagnostic services, trained personnel and treatment reach communities where transmission continues. Without sustained funding, improved security and effective contact tracing, the outbreak could remain a regional public health threat.
Health
Why Does the Brain’s Waste-Clearance Process Slow Down During Sleep As We Age?
A new MIT study finds that the movement of cerebrospinal fluid, which is involved in clearing waste from the brain, becomes weaker in older adults during sleep. The findings offer new insights into the relationship between ageing, sleep and brain health.

Sleep is often described as a period when the body rests and recovers. But the brain does not simply switch off when we fall asleep. It remains active, carrying out several processes that support its functioning, including the movement of fluid that helps transport waste products away from brain tissue. Now, researchers at the Massachusetts Institute of Technology (MIT) have found that this process becomes less pronounced with age. A study published in Nature Aging reports that older adults experience significantly weaker waves of cerebrospinal fluid (CSF) or brain waste clearance during sleep than younger adults.
Could changes in the brain’s waste-clearance processes help explain why the risk of cognitive decline and neurodegenerative diseases increases with age?
How Does Brain Waste Clearance Work During Sleep?
The brain produces metabolic waste as its cells carry out their normal activities. These waste products need to be transported away to maintain a healthy environment for brain cells. One of the fluids involved in this process is cerebrospinal fluid (CSF). It is a clear liquid that surrounds the brain and spinal cord, cushions them against injury, and helps maintain their chemical environment.
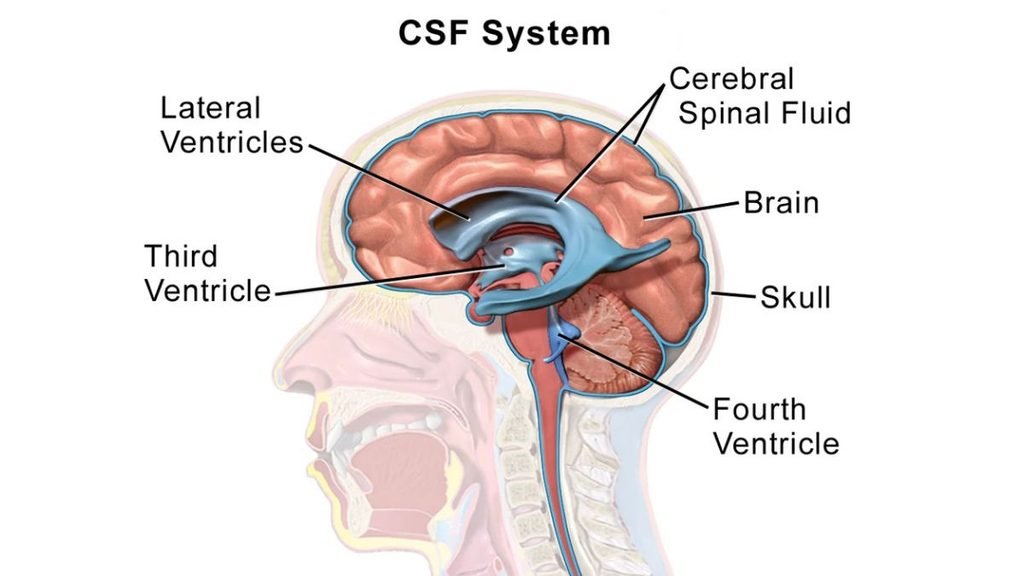
CSF also moves through spaces around brain tissue, contributing to the transport of substances and waste products. Scientists study this process in relation to the glymphatic system. The term describes a network of pathways through which fluid moves, facilitating the removal of waste from the brain.
During deep sleep, the brain produces slow, rhythmic electrical waves. These are associated with changes in blood volume, which in turn help generate waves of CSF movement. In simple terms, brain activity, blood circulation and fluid movement work together during sleep. Earlier research by MIT professor Laura Lewis and colleagues, published in Science in 2019, demonstrated how these slow brain waves are coordinated with changes in blood flow and CSF movement.
What Did the New Study Discover?
Building on their earlier work, the MIT researchers wanted to understand whether this process changes as people grow older. They recruited participants from two age groups: 18–39 years and 60–84 years. Using magnetic resonance imaging (MRI) and electroencephalography (EEG), they monitored brain activity, blood flow, and CSF movement while participants were in a scanner at night.
The researchers found that younger adults experienced stronger slow brain waves during non-rapid eye movement (NREM) sleep, accompanied by larger waves of CSF. Older participants, however, showed significantly smaller CSF waves. Importantly, the difference was not simply explained by older people sleeping for shorter periods. The researchers identified changes in the mechanisms that coordinate brain activity, blood circulation and fluid movement.
The study measured the movement and strength of CSF waves. It did not directly measure how much metabolic waste was removed from each participant’s brain. Therefore, weaker CSF waves suggest a potential impairment in a process involved in waste clearance, but do not establish that the brain actually removed less waste.
Why Does Blood Circulation Matter?
To understand what might cause the reduction in CSF movement, the researchers examined how blood vessels respond to changes in brain activity. Normally, when a part of the brain becomes more active, nearby blood vessels expand to supply additional oxygen and nutrients. This process is called neurovascular coupling.
The researchers showed participants a flickering checkerboard image to stimulate brain activity. Although older participants showed an increase in neural activity, their blood flow did not increase as much as it did in younger participants. In another experiment, participants were asked to hold their breath briefly. This raises carbon dioxide levels in the blood, normally prompting blood vessels in the brain to expand and increase blood flow.
Again, older participants showed a smaller increase in cerebral blood flow. These experiments suggest that blood vessels become less responsive with age. Since changes in blood volume help generate CSF waves during sleep, reduced vascular responsiveness may contribute to weaker fluid movement. However, the researchers found that these vascular changes did not explain the entire reduction. Other age-related factors may also be involved.
Does This Increase the Risk of Alzheimer’s Disease?
The findings are relevant to research on Alzheimer’s disease and other neurodegenerative disorders, which are associated with the accumulation of abnormal proteins and other changes in the brain. Earlier studies have linked disturbed sleep with an increased risk of cognitive decline and dementia. Researchers are interested in whether impaired fluid movement during sleep could be one of the mechanisms connecting sleep disturbances with brain health.
“We know that people age really differently. Some people age very successfully with great cognitive outcomes, and other people develop cognitive decline. If we can figure out who has great trajectories of aging and what are the factors that are associated with that, we might be able to use that to predict future outcomes,” says Laura Lewis, the Athinoula A. Martinos Associate Professor of Electrical Engineering and Computer Science, a member of MIT’s Institute for Medical Engineering and Science and the Research Laboratory of Electronics, and an associate member of the Picower Institute for Learning and Memory.
In the MIT study, some older participants showed signs of grey matter atrophy, or a reduction in brain tissue volume. This was associated with a greater decline in CSF movement. However, the study does not establish that reduced CSF movement causes grey matter loss, Alzheimer’s disease or dementia. None of the participants had been diagnosed with a neurodegenerative disorder. The researchers hope to follow some participants over time to investigate whether differences in CSF movement are associated with future cognitive outcomes.
Can the Process Be Improved?
The researchers are also exploring whether interventions could improve CSF movement during sleep. In an earlier study, Lewis’ laboratory found that short bursts of pink noise during sleep could increase CSF flow in younger adults. Pink noise is a type of sound in which lower frequencies carry more energy than higher frequencies. Whether the same intervention works in older adults has not yet been established.
Another important question is why some older participants in the new study retained CSF waves comparable to those of younger adults. Understanding what protects these individuals could help researchers identify factors associated with healthier brain ageing. For now, the findings offer a new perspective on the relationship between sleep and ageing. They suggest that the quality of sleep-related processes may matter alongside the amount of sleep a person gets. But whether improving CSF movement can actually prevent cognitive decline or reduce the risk of neurodegenerative diseases remains to be investigated.
Society
Intellectual disabilities linked to severe educational disadvantage in India, study finds
A new study published in Scientific Reports highlights significant educational disadvantages among people with intellectual and developmental disabilities and mental illness in India. Alongside school enrolment and infrastructure data, the findings underline persistent gaps in inclusive education, gender equality and access to learning support.

New Delhi: People with intellectual and developmental disabilities (IDD) in India face substantially greater educational disadvantages than those without disabilities, with gender and economic inequalities further widening the gap, according to a study published in Scientific Reports on October 15, 2026.
The research, analysed data from 402,994 adults using the 76th round of the National Sample Survey (NSS), conducted in 2018.
Researchers found that individuals with intellectual and developmental disabilities had a 71.3% predicted probability of receiving no formal education. The corresponding probability among people reporting mental illness was 48.3%.
The study also found that individuals with IDD had 28.9 times higher odds of receiving no formal education than those without disabilities. For individuals with mental illness, the odds were 3.3 times higher.
The findings highlight how disability-related barriers can translate into long-term educational exclusion, particularly when combined with poverty and gender discrimination.
Gender and economic inequalities compound exclusion
The researchers examined how educational disadvantages varied across gender and household economic groups.
Women with mental illness faced a particularly pronounced disadvantage. They were 18.7 percentage points more likely than men with mental illness to have received no formal education.
Economic circumstances also influenced educational outcomes. Among individuals with IDD, the predicted probability of receiving no formal education declined from approximately 79.9% in the poorest household group to 62.9% in the richest group.
For individuals with mental illness, the corresponding probability declined from approximately 59.9% to 33.5%.
However, economic advantage did not eliminate gender disparities. The researchers found that women with mental illness continued to experience educational disadvantages even in the wealthiest household category.
The study distinguishes between intellectual and developmental disabilities and mental illness, highlighting the importance of addressing their different educational and support requirements rather than treating them as a single category.
Enrolment figures reveal the scale of the challenge
The research findings gain significance when considered alongside India’s school-enrolment figures.
According to the Unified District Information System for Education Plus (UDISE+) data cited in a Lok Sabha response on March 30, 2026, approximately 1.91 million children with special needs were enrolled in government, government-aided and local-body schools during 2024–25.
The corresponding figure was approximately 1.93 million in 2023–24. Girls accounted for 827,521 of the enrolled children in 2024–25, representing approximately 43.4% of the total.
The figures indicate the scale of the population requiring inclusive educational support. However, enrolment alone does not establish whether children are receiving appropriate learning assistance, participating fully in classrooms or progressing through different levels of education.

Representational image.Image credit:Unsplash
Infrastructure and specialist support remain important components of inclusive schooling. The Ministry of Education’s Annual Report 2024–25 recorded that 11.34 lakh schools had ramps, 7.69 lakh had ramps with handrails and 5.06 lakh had children-with-special-needs-friendly toilets during 2023–24.
The government also reported 52,274 government, government-aided and local-body schools with special educators in 2024–25. These figures point to the need to assess not only school access but also the availability and distribution of trained personnel and accessible facilities.
Strengthening inclusive education
India’s Right of Children to Free and Compulsory Education Act, 2009, and the Rights of Persons with Disabilities Act, 2016, provide the legal framework for improving educational access for children with disabilities.
Under the Samagra Shiksha scheme, the government provides support through early identification, assessment, assistive devices, therapeutic interventions, transport allowances, resource support and individualised learning assistance.
The scheme also provides a stipend of Rs 200 per month for ten months to eligible girls with special needs to encourage school participation.
However, the research highlights the importance of addressing barriers that extend beyond school infrastructure and financial assistance. Teacher preparedness, social stigma, gender discrimination and inadequate access to specialised support can influence educational participation and attainment.
The researchers emphasise the need for gender-sensitive and income-sensitive interventions, including school-based mental-health support, community awareness programmes and stronger access to healthcare services.
The study also acknowledges limitations arising from its reliance on cross-sectional and self-reported data. Its findings establish associations rather than proving that disability alone causes educational exclusion. Moreover, because the analysis covers adults, it cannot directly measure the present-day enrolment or dropout rates of children with disabilities.
Nevertheless, the findings offer an important indication of how educational inequalities can persist into adulthood. They underline the need to strengthen inclusive education systems so that children with disabilities are not merely enrolled in schools but are also supported in completing their education and accessing further opportunities.

Challenge AI on Climate Science, and It May Abandon the Facts

India Records 436 Extreme Weather Events in 30 Years, Loss of 170 billion USD

Woxsen University Ranks 12th Globally in MBA Entrepreneurship Ranking, Fourth in Startup Launches

IIT Delhi Returns to Global Top 200 in QS Sustainability Rankings 2027; 38 Indian Universities Improve

India’s Clean-Energy Transition: Will It Replace Oil Dependence With Mineral Dependence?

Indian universities lead Asia in research output per faculty, but the country’s top six all slip in QS ranking

Why Delhi’s Geography Makes It Vulnerable to Severe Air Pollution

Europe Braces for Extremes as Commission Unveils Climate Resilience Framework

NASA recruits new astronauts for future Moon Base and Mars missions

Between Lectures and Lyrics: Kabeer Is Building a Malayalam Hip-Hop Career One Self-Taught Skill at a Time
-

 Math4 months ago
The 2026 Fields Medals: Four Proofs, Four Decades-Old Problems Solved
-
EP Deep Dive: Data & Solutions4 months ago
After Kerala’s Deadliest Landslide, the Hardest Thing to Rebuild Was Childhood
-
EP Deep Dive: Data & Solutions5 months ago
West Asia Crisis: Can Kerala’s Returning Gulf Migrants Find a Future in the Green Economy?
-
Space & Physics6 months ago
India Semiconductor Mission: ‘It’s Not About Fabs. It’s About Building An Entire Ecosystem’
-
Interviews2 months ago
From Scams to Screens: How the National Stock Exchange Rewrote India’s Equity Story
-
Climate & Environment6 months ago
The Climate World Cup? How Climate Change Could Affect Player Performance at the 2026 World Cup
-
Society4 months ago
What Is Civilisational Diplomacy? Understanding India’s Newest Foreign Policy Tool
-
Society5 months ago
From Bell Labs to the Classroom: A Second Career in Teaching















