
Health
Pancreatic Cancer Is Often Found Too Late. Scientists Want to Intercept It Earlier
More than 530,000 people develop pancreatic cancer globally each year. Researchers are exploring whether early detection and targeted drugs can stop it before it spreads.


More than half a million people are diagnosed with pancreatic cancer around the world each year. For many, the disease is discovered only after it has moved beyond the pancreas. The timing can make a profound difference. In the latest global estimates from the International Agency for Research on Cancer (IARC), more than 530,000 people developed pancreatic cancer in 2024, while more than 490,000 died from it. Although pancreatic cancer is only the 12th most commonly diagnosed cancer worldwide, it ranks sixth as a cause of cancer death.
It is also largely a disease of older adults. In the US, where detailed cancer surveillance data are available, the median age at diagnosis is 71. About two-thirds of patients are at least 65, according to the American Cancer Society.
But age is only part of the problem. Pancreatic cancer can remain difficult to recognise because early disease often causes no obvious symptoms. The pancreas sits deep inside the abdomen, making early tumours difficult to detect through a routine physical examination. When symptoms such as jaundice, weight loss, abdominal or back pain appear, the cancer may already have grown substantially or spread.
That is why researchers are beginning to pursue an idea that changes where the fight against pancreatic cancer starts. Instead of waiting for a tumour to become invasive, they want to identify the abnormal changes that come before it — and stop the disease there. The strategy is called cancer interception.
Why Catching It Early Matters
The numbers show why researchers are looking further upstream. In the latest US SEER data, only about 15% of pancreatic cancer cases are diagnosed while the cancer is still confined to the pancreas. For these patients, the five-year relative survival rate is 43.6%.
Once the cancer has spread to nearby lymph nodes, five-year survival falls to 17%. For patients whose cancer has already metastasised to distant parts of the body, it is just 3.4%. Overall, the five-year relative survival rate is 13.7%. Those figures are not simply statistics about treatment. They explain the urgency behind early detection. If doctors can find pancreatic cancer before it spreads, patients have a substantially better chance of surviving it.
The difficulty is that there is currently no routine screening test recommended for people at average risk. The American Cancer Society notes that no screening test has yet been shown to reduce deaths from pancreatic cancer in the general population. Surveillance is instead considered for people at particularly high risk, such as those with certain inherited genetic risks or strong family histories. So researchers are looking for people who can be watched closely before cancer appears.
Following People Before Cancer Arrives
One of the largest efforts is PRECEDE, a clinical study led by Diane Simeone, director of the Moores Cancer Center at the University of California San Diego Health. The study aims to follow 20,000 people at increased risk of pancreatic cancer. Participants include people with a family history of the disease, certain abnormalities in the pancreas and genetic factors that raise their risk.
More than 12,000 people had enrolled by the time researchers presented an update at the American Association for Cancer Research conference on pancreatic cancer in September. More than 50 pancreatic cancers had been detected among participants, many at early stages.
That makes the study more than an exercise in surveillance. It is creating a group of people who can be followed closely as their pancreatic tissue changes, potentially allowing researchers to see what happens in the period between an abnormality and full-blown cancer.
The researchers are also collecting biological samples to study experimental blood tests that could detect pancreatic cancer earlier. And there is another tool they hope can help: artificial intelligence. Researchers are examining whether AI can identify subtle abnormalities in pancreatic scans before they become apparent to the human eye.
If these approaches work, the goal would be to move diagnosis forward, from the point at which cancer is already established to a much earlier stage in its development. But early detection creates a new question. If doctors find something that could become cancer, can they stop it?
Can the Drug Work Earlier?
A new targeted drug has given scientists another reason to investigate. In August, the US Food and Drug Administration approved daraxonrasib for certain patients with advanced pancreatic cancer. The drug targets KRAS, a protein involved in signals that can drive cancer growth.
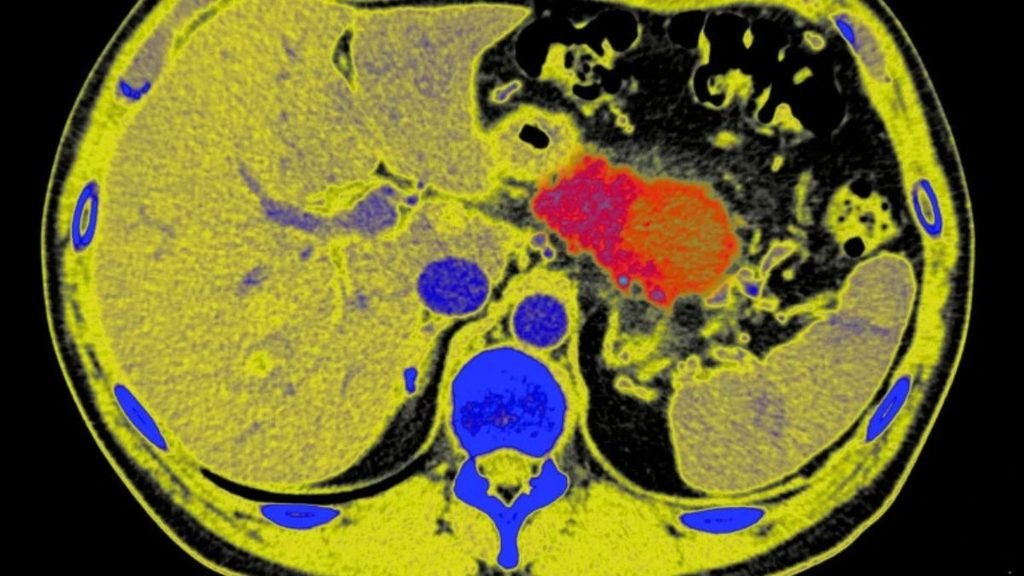
In a randomized clinical trial involving 500 patients with advanced pancreatic cancer, median overall survival was 13.2 months for patients receiving daraxonrasib, compared with 6.7 months for those receiving standard chemotherapy.
But the drug’s approval does not mean it can prevent pancreatic cancer.
It is approved for advanced disease. Researchers are interested in what might happen if drugs that target cancer-driving pathways are used much earlier, perhaps when abnormal pancreatic cells have not yet developed into an invasive tumour. That is the central idea behind interception.
Stopping Cancer Early
Treating someone who already has metastatic cancer and treating someone who has a precancerous pancreatic abnormality are completely different medical decisions. For a patient with advanced cancer, the potential benefits of a powerful treatment may justify significant side effects. For someone who has an abnormality that might never become cancer, the calculation is different.
Researchers therefore need to know which precancerous changes are dangerous enough to treat and whether the treatment itself causes more harm than the disease it is intended to prevent. That is why much of the evidence for pancreatic cancer interception is still coming from laboratory and animal studies.
A clue From Mice
At the September AACR meeting, Ben Stanger, a cancer researcher at the University of Pennsylvania, and his colleagues presented research involving mice carrying mutations in the Kras gene. KRAS mutations can activate proteins that promote cancer development. The researchers waited until the mice developed tiny precancerous growths in the pancreas. They then treated the animals with a drug designed to interfere with KRAS and related cancer-promoting proteins.
The treatment improved survival in the mice. The finding matters because it suggests that cancer-driving pathways may be vulnerable even before a pancreatic tumour becomes invasive. The researchers still need to establish whether the same strategy is safe and effective in humans, which patients should receive it, and how early treatment should begin.
From Treating Cancer to Stopping Its Progression
This is what makes cancer interception such a significant shift in pancreatic cancer research. The traditional approach begins after a tumour has formed. Doctors then try to remove it, shrink it or keep it from spreading. Interception moves the starting line. Researchers want to identify the biological changes that put pancreatic cells on the path toward cancer and intervene before that process becomes difficult to reverse.
Simeone’s team is already considering whether therapies such as daraxonrasib could eventually be studied in people after surgery for precancerous pancreatic growths or in patients with very early-stage disease. Such use would require clinical trials; the drug is currently approved for advanced pancreatic cancer. Simeone has estimated that combining earlier detection with interception could potentially raise five-year survival from 13.7% to 50%.
That figure is a research projection, not a demonstrated result.The immediate challenge is much more basic: scientists need to prove that they can reliably identify dangerous pancreatic changes early enough, and that treating them will actually prevent cancer from progressing.
For a disease in which only about 15% of cases in current US data are found while still localized, even finding that window would change the problem researchers are trying to solve. The hope behind cancer interception is therefore not simply to find a better drug for pancreatic cancer. It is to change the moment at which doctors have to fight it, from after it has spread to before it has a chance to become invasive.











Health
What is the Mysterious ‘Egoviruses’ in the Guts of 180 Million People
Scientists have discovered egoviruses, a previously unknown group of gut viruses potentially present in 180 million people worldwide. Their genetic connection to poxviruses could offer new clues about viral evolution.

Millions of people could be carrying a previously unknown group of disease-causing viruses in their digestive systems without ever knowing it. Scientists have now identified these microbes, named ‘egoviruses’, in human and animal gut samples, uncovering a surprising connection to one of the most important families of disease-causing viruses.
The discovery is drawing attention because egoviruses are closely related to poxviruses, the family that includes the viruses responsible for smallpox and mpox. Researchers estimate that these newly identified viruses could be present in around 180 million people worldwide. The findings offer a new perspective on the evolution of viruses and the largely unexplored microbial world inside the human digestive system.
Hidden Viral Population in the Human Gut
The discovery emerged from an extensive examination of genetic material collected from human and animal digestive systems. Rather than isolating individual viruses in laboratories, researchers used metagenomics, a technique that allows scientists to identify organisms by analysing genetic material in biological samples.
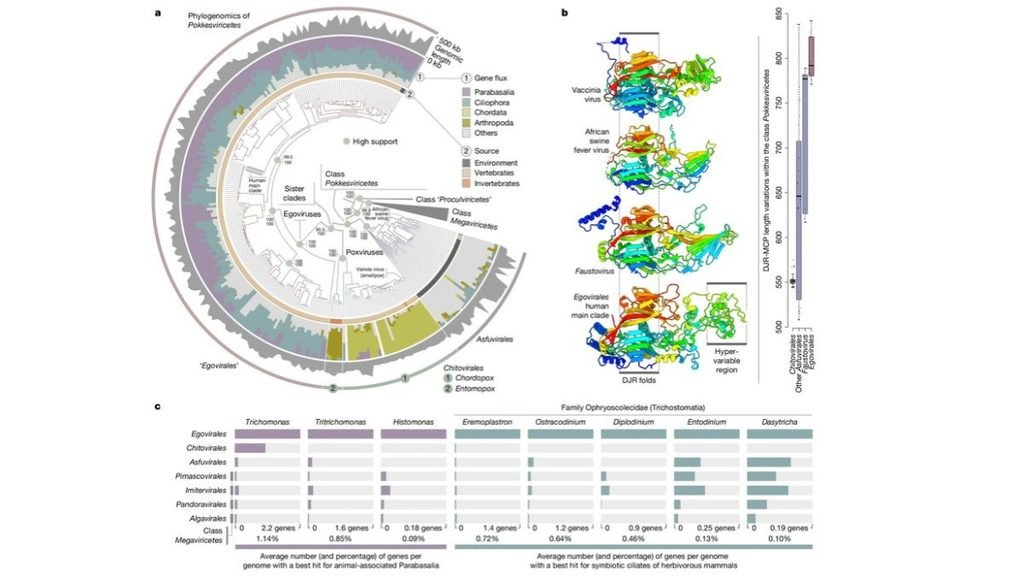
The research team, led by microbial ecologist Tom Delmont of the French National Centre for Scientific Research, identified egoviruses across samples from several countries. These included Tanzania, Nepal, Fiji, the United States and parts of Europe.
The analysis revealed six distinct groups associated with humans. One of these groups was found across multiple continents, suggesting that the viruses are not confined to a particular population or geographical region. The researchers also detected egoviruses in buffaloes, goats, chickens, deer and pigs. Their presence across different animal species points to a much wider distribution than scientists had previously recognised.
Do These Viruses Actually Infect Humans?
If egoviruses are found in human gut samples, does that mean they infect human cells? Not necessarily. The researchers suspect that these viruses may target single-celled organisms living in the digestive tract rather than human cells themselves. Genetic comparisons revealed similarities between egovirus genes and those of two groups of single-celled organisms, Parabasalia and Trichostomatia.
Some members of these groups live in animal digestive systems. Trichostomatia, for example, includes microorganisms found in the digestive tracts of ruminants, where they are involved in breaking down food. This could mean that the human gut contains viruses that interact with its microbial inhabitants rather than directly attacking human tissue. However, researchers have yet to confirm their suspected hosts through direct experiments. There is also no evidence from this study that egoviruses cause illness in humans.
Surprising Link to Smallpox and Mpox Viruses
Perhaps the most intriguing aspect of the discovery lies in the evolutionary history of egoviruses. The researchers found that these viruses are the closest known relatives of poxviruses among the groups they examined. Poxviruses are large DNA viruses that can infect humans and animals. Smallpox, eradicated in 1980, and mpox belong to this family.
The genetic relationship has led researchers to investigate whether the ancestors of poxviruses once infected single-celled organisms before evolving the ability to infect animal cells. One possibility is that an ancestral virus initially lived among microorganisms in the digestive systems of early animals. Over millions of years, evolutionary changes may have enabled some descendants to infect animal cells directly.
This remains a hypothesis, rather than a confirmed account of how poxviruses originated. Nevertheless, egoviruses offer scientists a previously unknown group of viruses through which to investigate that evolutionary transition.
What Scientists Still Need to Find Out
The discovery adds another layer to the growing understanding of the human gut, which hosts a complex community of bacteria, fungi, viruses and other microorganisms. But identifying a virus is only the beginning. Scientists still need to establish which organisms egoviruses infect, how they behave inside the gut and whether they influence the wider microbial community.
For now, the discovery of a virus group potentially carried by 180 million people raises a fascinating possibility, a large part of the human body’s viral diversity may have remained hidden simply because scientists had not yet known where to look.
Health
India’s medical students show interest in research, but mentorship and institutional support remain major hurdles
A new review highlights the barriers facing Indian medical students pursuing research, including inadequate mentorship, limited funding and insufficient institutional support, despite strong student interest.

Indian medical students recognise the importance of research in strengthening healthcare, but many struggle to translate that interest into actual research projects and publications. Limited faculty mentorship, inadequate funding, insufficient research training and the pressure of academic workloads continue to restrict undergraduate research participation, according to a review published in Frontiers in Medicine on November 13, 2026.
The review, titled Understanding Research Orientation and Practice Among Undergraduate Medical/Dental Students in India: Challenges, Barriers and Enablers examines existing studies on undergraduate research engagement and evaluates national initiatives intended to develop research capabilities among medical and dental students.
The findings point to a gap between students’ willingness to pursue research and the institutional support available to help them do so.
Research interest does not translate into participation
A 2024 cross-sectional study involving 606 Indian medical students found that awareness of research opportunities did not necessarily translate into completed projects.
Although 77.23% of respondents knew about the Indian Council of Medical Research’s (ICMR) Short-Term Studentship (STS) programme, only 16.34% had applied. Just 6.4% completed their research within the prescribed period, while only 1.98% published their ICMR-related findings.
The study also examined students’ access to academic guidance. While 65.35% approached faculty members for assistance, only 46.53% found them helpful. Just 33.17% received assistance from senior students.
The findings suggest that awareness campaigns alone may not be sufficient to develop a research culture without accessible mentorship and sustained institutional support.
The 2026 review also highlights findings from individual medical colleges. At ESIC Medical College, Chennai, a study involving 241 students found that only 8.3% actively participated in research, despite 60% recognising its importance in clinical care.
At Pushpagiri Institute of Medical Sciences and Research Centre in Kerala, a study of 160 undergraduate students and interns found that 96.9% recognised the value of research, but only 12.5% had participated in ICMR-STS.
These institution-specific findings illustrate the difference between research awareness and actual engagement.
A wider institutional research gap
The challenge extends beyond undergraduate classrooms. A study examining research output across 579 Indian medical institutions, cited in a 2026 research paper, found that 57.3% had no publications.
The finding raises questions about the research environment in medical institutions and the opportunities available to students who want to participate in scientific investigation.
However, some institutions have demonstrated that structured mentorship can improve participation.
A study published in BMC Research Notes in April 2026 documented the experience of JIGNYASA, a student-led undergraduate research committee established in February 2020 at a government medical college and tertiary-care hospital in western India.
Between February 2020 and September 2025, the initiative recorded 228 student-initiated research projects, 34 grant approvals and 59 publications.

A medical student examining a report.Image credit:Pexels
The model relied on senior-student mentorship, continuous faculty guidance, research-promotion activities and regular feedback. The authors presented it as a potentially replicable approach for institutions seeking to strengthen undergraduate research without substantial additional funding.
National programmes need stronger implementation
The Frontiers review examines three initiatives: ICMR’s Short-Term Studentship programme, the National Medical Commission’s Community Health Programme and the Basic Course in Biomedical Research.
The STS programme provides undergraduate medical and dental students an opportunity to undertake short-term research under faculty supervision. The Community Health Programme introduces students to field-based health research, while the Basic Course in Biomedical Research provides structured training in research methodology.
However, the review identifies limitations, including inadequate research grants, uneven access to mentors, limited hands-on training and insufficient support for publishing findings.
It argues that medical colleges need to provide dedicated research time, accessible funding, trained faculty mentors and stronger institutional research infrastructure.
For India, developing clinician-researchers is important not only for improving medical education but also for strengthening the country’s capacity to generate evidence relevant to its own healthcare needs.
The evidence suggests that the problem is not simply a lack of interest among medical students. It is the absence of consistent opportunities and institutional structures that can turn that interest into meaningful scientific contributions.
Health
Six months on, Ebola outbreak in DR Congo remains uncontrolled, with over 5,500 deaths
Six months after its declaration, the Ebola outbreak in DR Congo remains uncontrolled, with over 5,500 deaths. Armed conflict, gaps in disease surveillance and limited healthcare access continue to hamper containment efforts as the Bundibugyo virus spreads across eight provinces.
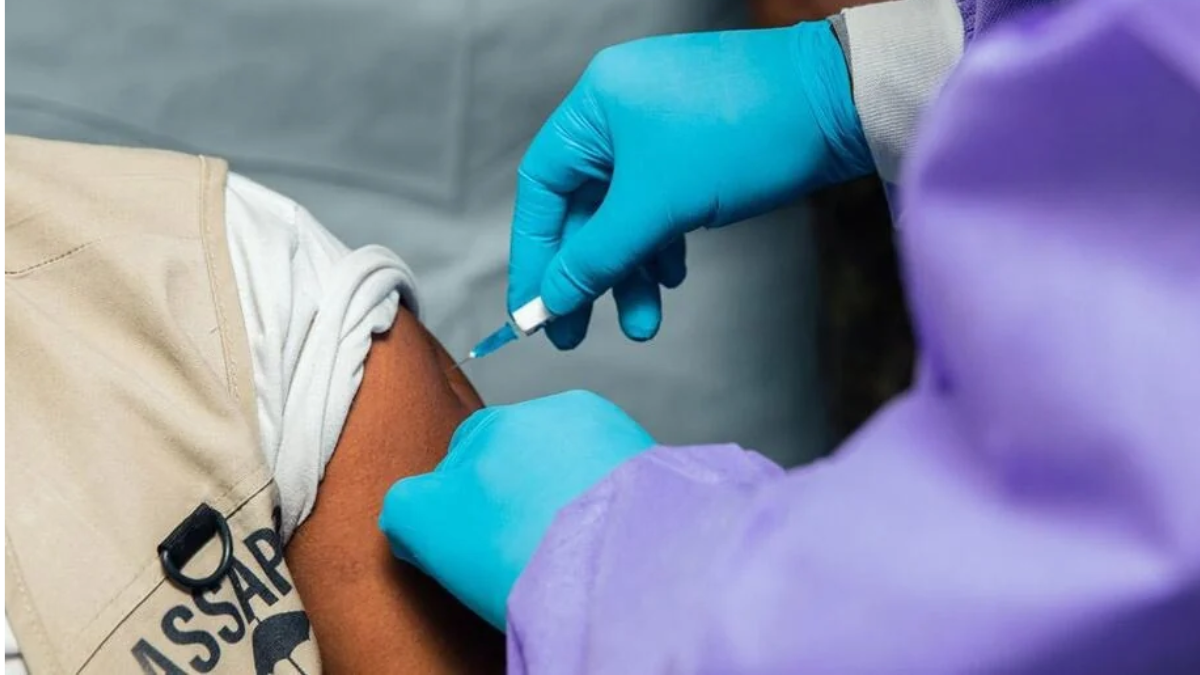
Six months after the Democratic Republic of the Congo (DRC) declared an Ebola outbreak, the disease remains out of control, with more than 11,300 confirmed cases and 5,500 deaths reported in the country. Despite an expanded international response, the outbreak continues to spread amid armed conflict, displacement and weaknesses in healthcare delivery.
The Africa Centres for Disease Control and Prevention (Africa CDC) warned on November 15 that the outbreak was still not under control. Its Director-General, Jean Kaseya, cautioned that unless transmission is interrupted, the epidemic could become the world’s worst Ebola outbreak.
According to the European Centre for Disease Prevention and Control (ECDC), the DRC had recorded 11,376 confirmed infections and 5,568 deaths as of November 15, based on data up to November 14. Eight provinces have been affected, with Ituri reporting the highest burden. The outbreak is caused by the Bundibugyo virus, a relatively rare species of Ebola virus.
Delayed detection is driving transmission
One of the biggest obstacles to containment is the inability to identify infected people and their contacts early. According to Africa CDC, more than 80% of new infections are being detected among people who were not previously listed as contacts of confirmed patients.
Contact tracing is central to Ebola control. Once an infection is confirmed, health workers identify people who may have been exposed and monitor them for symptoms during the 21-day incubation period. Failure to identify these contacts creates opportunities for further transmission.
More than 65% of deaths have occurred in communities rather than healthcare facilities, indicating that many patients are being identified too late to receive timely treatment. The World Health Organization (WHO) reported that children account for more than a quarter of confirmed infections and approximately one-third of deaths. Seven in 10 children under five who contract the disease have died.
The outbreak has expanded to 67 health zones across eight provinces, with an estimated 400–500 new cases being reported each week, according to the WHO’s November 14 update.
Conflict and insecurity disrupt response
Armed conflict and population displacement have further complicated containment. Insecurity has restricted access to affected communities, disrupted healthcare services and made surveillance and contact tracing difficult.
The WHO reported more than 80 attacks on healthcare since the outbreak began. An armed attack in Cantine-Aloya killed 66 civilians, including three health workers, while three healthcare facilities were looted. More than 1,000 contacts were subsequently lost to follow-up, and three confirmed patients could not be accounted for.
The response has also been affected by delayed payments to frontline health workers. Africa CDC has warned that inadequate resources, insufficiently trained personnel and operational difficulties are weakening efforts to contain the disease.

To help fight the spread of Ebola, UNICEF is supporting District Health Educators (DHE) in high-risk districts to conduct outreach activities with different groups, including corporate and business sectors, educational facilities, prisons, hostels and guest-houses. Photo: UNICEF/UNI790701/Bamulanzeki
Healthcare capacity expands, but gaps persist
There has been progress in strengthening the response. According to the WHO, diagnostic capacity has increased from two laboratories to more than two dozen, while nearly 2,000 treatment beds have been made available across 104 treatment and transit centres.
More than 17,000 community health workers and 46,000 community actors have received training to support surveillance, contact tracing and public awareness. Nearly 90% of registered deaths are now being managed through safe and dignified burials, reducing the risk of transmission during funerals.
However, these improvements have not translated into nationwide containment. Several initial outbreak centres, including Butembo, Mongbwalu and Nyankunde, have brought transmission under control, but new infections continue to emerge elsewhere.
The challenge of containing Bundibugyo virus
The virus itself presents another challenge. Bundibugyo is distinct from the Zaire ebolavirus responsible for the 2014–2016 West African epidemic. Vaccines developed against the Zaire species cannot be assumed to protect against Bundibugyo virus. There is currently no licensed vaccine specifically approved against this strain.
The international response therefore continues to depend on early diagnosis, isolation, supportive treatment, infection prevention and safe burial practices, alongside research into candidate vaccines and treatments.
The WHO has called for sustained, flexible funding through 2027 and improved access to communities affected by conflict. The outbreak has also prompted stronger cross-border surveillance, following infections reported in Kenya and Nigeria.
Six months into the crisis, the challenge is no longer simply mobilising an emergency response. It is ensuring that diagnostic services, trained personnel and treatment reach communities where transmission continues. Without sustained funding, improved security and effective contact tracing, the outbreak could remain a regional public health threat.

The Science of Selling: How Sudheer Babu Decodes Buyer Psychology in ‘The Revenue Multiplier’

What Declining Freshwater Storage Means For India?

Pune to Host India International Science Festival 2026, With Focus on Students, Startups and Public Engagement

What Can Himalayan Marmot Droppings Tell Us About Climate Change?

$71 Billion Carbon Market, but Only $1.6 Billion in Government Deals: COP31 Exposes Gap Between Carbon Credit Supply and Demand

Indian universities lead Asia in research output per faculty, but the country’s top six all slip in QS ranking

Why Delhi’s Geography Makes It Vulnerable to Severe Air Pollution

India’s Richest Agree on One Cause Above All Others: Education

Europe Braces for Extremes as Commission Unveils Climate Resilience Framework

NASA recruits new astronauts for future Moon Base and Mars missions
-

 Math4 months ago
The 2026 Fields Medals: Four Proofs, Four Decades-Old Problems Solved
-
EP Deep Dive: Data & Solutions4 months ago
After Kerala’s Deadliest Landslide, the Hardest Thing to Rebuild Was Childhood
-
EP Deep Dive: Data & Solutions5 months ago
West Asia Crisis: Can Kerala’s Returning Gulf Migrants Find a Future in the Green Economy?
-
Space & Physics6 months ago
India Semiconductor Mission: ‘It’s Not About Fabs. It’s About Building An Entire Ecosystem’
-
Interviews2 months ago
From Scams to Screens: How the National Stock Exchange Rewrote India’s Equity Story
-
Climate & Environment6 months ago
The Climate World Cup? How Climate Change Could Affect Player Performance at the 2026 World Cup
-
Society4 months ago
What Is Civilisational Diplomacy? Understanding India’s Newest Foreign Policy Tool
-
Society5 months ago
From Bell Labs to the Classroom: A Second Career in Teaching















