
Health
What Forests Could Hold for the Future of Cancer Treatment
Cancer treatment has benefited from plant-derived compounds, including medicines used against leukaemia, lymphoma, breast and ovarian cancers. But deforestation could destroy plants that may contain compounds with potential for future drug discovery.


Cancer remains one of the biggest challenges in medicine. While treatments have improved significantly, there is no single cure for cancer, and some cancers remain difficult to treat. Researchers continue to look for drugs that can target cancer cells more effectively and overcome treatment resistance.
cancer treatment medicines used today were developed from compounds found in plants. Researchers are still studying plants for molecules that could be developed into new drugs. But deforestation could reduce the number of species available for this research, a new analysis suggests.
An analysis by Zero Carbon Analytics estimates that tropical forests contain about USD 714 billion in potential commercial pharmaceutical discovery value from flowering plants. It estimates that deforestation between 2001 and 2024 has already put about USD 86 billion of this potential value at risk. The finding is relevant to cancer research because natural products have contributed to several cancer medicines.
Cancer Medicines From Plants
The link between forests and cancer treatment is already well established. Vincristine and vinblastine, derived from the Madagascar periwinkle, are used against leukaemia, lymphoma and other cancers. Paclitaxel, first isolated from the Pacific yew, is used to treat cancers including breast and ovarian cancer. Camptothecin, from Camptotheca acuminata, led to the development of the cancer drugs irinotecan and topotecan.
Their contribution is part of a wider pattern. A review found that about 25% of anticancer drugs approved between 1981 and 2019 were related to natural products. Zero Carbon Analytics reports that three in four cancer drugs discovered between 1940 and 2014 were natural products, derived from them or inspired by them.
The Research Gap
The bigger concern is what forests could still offer cancer treatment research in the future. The analysis calls this “option value” — the value of keeping open the possibility of discovering new medicines from plants that have not yet been studied.
That possibility is large. The analysis estimates that 99% of plant compounds remain unexplored and that tropical forests could contain around 328 plant-derived drugs with potential commercial value, although the estimate ranges from 200 to 460.
These are not 328 ready-made cancer drugs. Most compounds found in plants will not become medicines and must first go through laboratory tests, safety checks and clinical trials.

But once a species is lost before scientists study it, that opportunity may be lost too. For cancer research, deforestation could therefore mean losing potential sources of new cancer treatments before researchers know what they contain.
What This Means For The Western Ghats?
India’s Western Ghats shows how much remains to be studied. A 2025 review recorded 1,628 medicinal plant species used traditionally in the region, but only 115 had been validated through scientific studies or clinical use.
Some are already being tested for possible cancer-related properties. A 2025 study of Tarenna alpestris, a plant from the Megamalai Hills, found anticancer activity against colon cancer cells in the laboratory.
This does not mean the plant can treat cancer. More research is needed to identify the active compounds and test their safety and effectiveness. But it shows how plants can enter the early stages of cancer-drug research.
Why Forest Loss Matters To This Research
Deforestation can remove species before researchers have a chance to study them. The Zero Carbon Analytics analysis estimates that continued deforestation could put USD 174 billion in potential pharmaceutical value at risk by 2050. Stopping deforestation by 2030 could preserve about USD 79 billion of that potential value.
These figures are about possible drug discoveries, not confirmed cancer treatments. For cancer research, the concern is simpler: losing forests could mean losing plants and compounds that might lead to new anticancer drugs.
Technology can help scientists study natural compounds, but it cannot replace species or compounds that were never studied. Natural products are only one part of cancer-drug research, but the history of vincristine, vinblastine, paclitaxel and camptothecin shows that they have already contributed to cancer treatment. The question is how much potential could be lost before researchers get the chance to study it.









Health
Not Broken but Unheld: A New UN Report Asks Us to Tend the Forest, Not Only the Tree
A new UN report on youth mental health calls for an ecosystem approach linking well-being with education, work, housing, climate, technology and community.

Health
Ebola Outbreak Worsens in DRC as WHO Calls for Urgent Patient Care
More than 8,000 cases have been reported in the Democratic Republic of the Congo, while limited access to treatment and ongoing violence are complicating efforts to contain the outbreak.

The Democratic Republic of the Congo (DRC) is facing its largest-ever Ebola outbreak, with more than 8,000 cases reported, according to health authority data published on Monday. The World Health Organization (WHO) has called for faster access to medical care as delays in treatment continue to contribute to deaths. While transmission has begun to decline in some areas, the number of cases remains high, WHO officials said.
With 8,067 confirmed cases and 3,901 deaths, the case fatality rate is more than 48 per cent in 63 affected health zones in seven out of DRC’s 26 provinces. “While we are beginning to see a reduction in transmission in some areas, the number of cases remains high for this outbreak,” Dr Janet Diaz of the WHO Health Emergencies Programme told reporters in Geneva. WHO and its partners have expanded Ebola treatment facilities across the affected regions.
Treatment capacity has increased from only a handful of beds at the beginning of the outbreak to more than 1,600 beds across 50 treatment centres in seven affected provinces. Authorities plan to increase the capacity to more than 2,000 beds. Nearly 400 health workers have also been trained as part of the response, with a training hub established in Bunia. Health workers are particularly important in Ebola treatment because patients require specialised care and close monitoring. “Every patient bed requires a skilled workforce to provide safe, quality care around the clock,” Diaz said.
Erupting Violence Amid Health Concerns
Amid the growing Ebola crisis,Aid teams have raised concerns about the situation at Kigonze displacement camp in Bunia, in northeastern Ituri province. According to reports, soldiers entered the heath camp searching for weapons and people suspected of links to non-State armed groups. Gunshots were also reported. The violence has added another challenge to efforts to control the Ebola outbreak, as displacement can make it harder for people to access healthcare and for response teams to trace and monitor cases.
According to the UN aid coordination office, OCHA, the camp hosts nearly 19,000 displaced people. Residents have faced “armed violence, threats and intimidation against civilians, arrests, forced displacement and the destruction of shelters”, the Office said. Echoing those concerns, UN Humanitarian Coordinator in the DRC, Damien Mama, said that many families had left the site to seek refuge with host families.
Mr. Mama also stressed that the civilian character of the site must be preserved and that families “who have already lost everything” must be able to find safety and dignity where they have find refuge. The dispersal of families also raises serious public health concerns, as Kigonze is among the sites covered by the ongoing Ebola response.
In Need of an Efficient System
Oxygen is another major challenge. It is an important part of supportive treatment, particularly for patients suffering from severe Ebola disease, but remains unavailable or unreliable at many health facilities, especially in emergency settings.
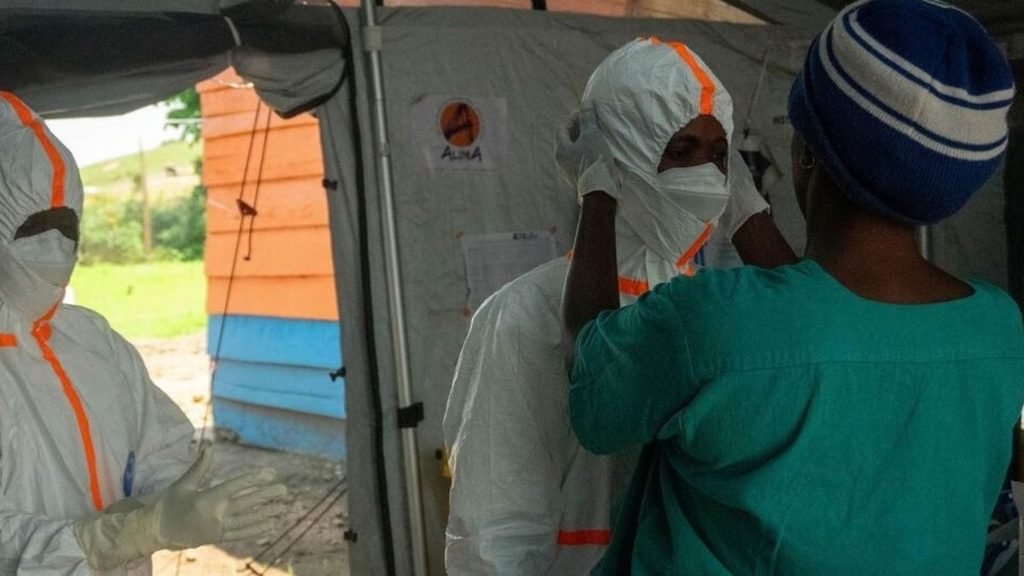
According to WHO, improving oxygen access requires more than supplying cylinders and equipment. It also depends on reliable infrastructure, trained healthcare workers and systems capable of delivering oxygen to patients when and where it is needed. There is currently no approved vaccine specifically for Ebola Bundibugyo virus, although vaccine trials are underway.
WHO has allocated 20,000 doses of the Ervebo vaccine for a research vaccination programme in Ituri province. The vaccine has previously been used against Ebola Zaire virus. WHO and its partners continue to focus on early detection, rapid referral, supportive treatment and improving access to healthcare as they work to contain the outbreak. “Delays in seeking care, together with challenges in access and referral, continue to complicate the response,” Diaz said.
Health
Worms in Tuna? Why a Brazil Study Has Triggered an Indian Advisory
A Brazil study found parasites in 51 of 53 skipjack tuna, including some in muscle tissue. CMFRI says the finding should not be applied to Indian tuna.

Is tuna safe to eat? That question has gained attention after a study from Brazil found a high prevalence of parasites in skipjack tuna. The researchers found parasites in 51 of 53 fish they examined. More importantly, some of the parasites were found in the muscle tissue, the part of the fish that people eat. The finding raised a food-safety concern. Some fish parasites, including Anisakis, can infect humans when contaminated seafood is eaten raw or inadequately cooked. This makes the presence of parasites in edible fish tissue more than a biological curiosity.
The concern has also reached India, where tuna is widely consumed. But the Brazilian study was conducted on fish caught in the Atlantic Ocean off Brazil. It does not tell us how common these parasites are in tuna caught in Indian waters. That distinction is now at the centre of an advisory from the ICAR-Central Marine Fisheries Research Institute (ICAR-CMFRI), Kochi.
What did the Brazil Study Find?
Researchers examined 53 skipjack tuna (Katsuwonus pelamis) caught off the Brazilian coast. Parasites were found in 51 fish, or 96% of the sample. The researchers recorded more than 1,500 parasites. They included Anisakis and parasites belonging to the Trypanorhyncha group.
The finding that drew the most attention was their presence in muscle tissue. Parasites were detected in the muscle of 31 fish, accounting for 58.5% of the sample. This is relevant to consumers because the muscle is the part of the fish that is normally eaten.
The researchers also pointed to the importance of removing the internal organs soon after the fish is caught. Proper handling can help reduce the movement of parasites from the viscera into the muscle.
Why did this Raise Questions in India?
The concern is easy to understand. If parasites can occur in the flesh of skipjack tuna, consumers may wonder whether the same thing happens in tuna sold in India. Parasite prevalence can differ between geographical regions. It can also depend on local ecological conditions and the availability of intermediate or secondary hosts such as copepods, according to CMFRI.

The study therefore does not establish that Indian tuna has the same parasite prevalence as the Brazilian sample.
What does CMFRI Say?
CMFRI has advised consumers not to avoid tuna or other commercially available fish simply because parasites have been reported in fish from a particular region. The institute says fish examined along the Indian coast, including tuna, have not shown external manifestations of harmful parasitic infestation.
CMFRI also says its scientists regularly examine fish, including skipjack tuna, for abnormalities and parasites. “Scientists at CMFRI regularly examine fish, including skipjack tuna, as part of fish biology studies and observe fish for abnormalities and parasites whenever necessary. The fish examined do not show external manifestations of harmful parasitic infestation,” said Dr Grinson George, Director, ICAR-CMFRI.
What Should Consumers Do?
CMFRI recommends proper handling and cleaning of fish. Prompt removal of the intestines and other viscera is important during processing. Thorough cooking provides another layer of protection. CMFRI says proper cooking kills parasites and significantly reduces the associated food-safety risk.
The concern is greater with raw or lightly cooked seafood. In such cases, the parasite burden of the particular fish and how it has been processed become important factors.
For Indian consumers, the Brazilian study is not evidence that Indian tuna is unsafe. The more immediate lesson is about food handling. Clean fish properly, remove the viscera promptly and cook it thoroughly. There is no need to avoid tuna solely because parasites were reported in fish from Brazil.


Icnoic Matterhorn Almost Snow-Free as Record Heat Accelerates Swiss Glacier Loss

Who Cares for India’s Older People?

Climate Change Is Already on Your Dinner Table. Here Is How It Got There

India Records Driest Monsoon in 11 Years as Rainfall Deficit Hits 12.6%

Not Broken but Unheld: A New UN Report Asks Us to Tend the Forest, Not Only the Tree

From Scams to Screens: How the National Stock Exchange Rewrote India’s Equity Story

Farmers Borrowed to Build ‘Diggis’. Two Years Later, They Are Still Waiting for the Subsidy

Aim for the Stars: Anjali Thomas’s Journey from a Small College in Kerala to the Frontiers of Medical Imaging

Anxiety Freezes Career Decisions. Curiosity Unfreezes Them

The Engineer of Tomorrow Is Already Here

-

 Math2 months ago
The 2026 Fields Medals: Four Proofs, Four Decades-Old Problems Solved
-
Climate2 months ago
After Kerala’s Deadliest Landslide, the Hardest Thing to Rebuild Was Childhood
-
Society3 months ago
West Asia Crisis: Can Kerala’s Returning Gulf Migrants Find a Future in the Green Economy?
-
Space & Physics4 months ago
India Semiconductor Mission: ‘It’s Not About Fabs. It’s About Building An Entire Ecosystem’
-
Interviews1 week ago
From Scams to Screens: How the National Stock Exchange Rewrote India’s Equity Story
-
Climate4 months ago
The Climate World Cup? How Climate Change Could Affect Player Performance at the 2026 World Cup
-
Society3 months ago
What Is Civilisational Diplomacy? Understanding India’s Newest Foreign Policy Tool
-
Society4 months ago
From Bell Labs to the Classroom: A Second Career in Teaching














