
Health
Scientists Find Two Distinct Origins in the Developing Human Brain
Brain cells in the forebrain and hindbrain develop from two distinct groups of early cells, Stanford researchers have found, revealing an ancient split that could improve research into brain-stem diseases such as SMA and ALS.

The human brain looks like one organ. Its history may tell a different story. A Stanford Medicine study has found that the front and back of the developing brain arise from two separate populations of brain cells, following different developmental paths from the earliest stages of embryonic development.
The finding challenges a long-standing idea that the entire brain grows from a common pool of progenitor cells. It may also solve a problem that has frustrated researchers for years: why some of the neurons that keep us breathing and swallowing have been so difficult to grow in the laboratory. The study was published in Nature Neuroscience on September 18.
Two paths, One Brain
Long before a brain takes shape, its cells begin making choices about what they will become. The Stanford researchers found that one group of early cells, carrying the Otx2 gene, develops into the forebrain and midbrain. A different group, marked by Gbx2, develops into the hindbrain. The two groups do not merge.
They also carry different arrangements of chromatin, the material that packages DNA. Those differences help keep the cells on separate developmental tracks. The hindbrain is not a minor part of the brain. It contains the brain stem and controls functions that keep the body running without conscious effort — breathing, heartbeat, swallowing and other basic processes.
Its neurons are also involved in moving the muscles of the face, tongue and throat. Yet scientists have struggled to make these cells from human stem cells. The new study suggests they may have been starting from the wrong place.
“People are always focused on creating the final cell type, like the neuron,” said Rayyan Jokhai, a graduate student and co-first author of the study. “But it’s important to begin at the earliest stages of embryonic development.”
Brain Cells: From Stem Cells to Working Neurons
The researchers used what they learned about early development to guide human pluripotent stem cells toward a hindbrain fate. It worked. The resulting neurons produced electrical signals and carried molecular markers associated with hindbrain regions involved in facial movement and swallowing.
For researchers studying brain-stem diseases, having these cells in the laboratory could be valuable. In spinal muscular atrophy, motor neurons progressively deteriorate. ALS can damage motor neurons in both the forebrain and hindbrain. As the disease progresses, patients can lose the ability to swallow and, eventually, breathe.
Scientists cannot simply take brain-stem tissue from living patients and watch these neurons deteriorate. Lab-grown human hindbrain neurons could provide another option: researchers can study the cells, investigate what goes wrong and test possible treatments.
An Ancient Split
The story gets older when the researchers look beyond humans. They found the same two-origin pattern in chickens and zebrafish. They also found it in acorn worms, distant relatives of humans.
The pattern appears to reach back more than 550 million years. That suggests the separation is not a recent feature of the human brain. Instead, it may be a very old arrangement inherited from ancestors that lived hundreds of millions of years ago. The researchers propose that evolution brought two ancient neural systems together, eventually producing the integrated brain seen in vertebrates. In other words, what looks like one organ may have a much more complicated family history.
More than a story about brain evolution The finding could reshape how scientists make specialised brain cells in the laboratory. It may also open another line of research. The hindbrain contains neural circuits involved in hunger and appetite, raising questions about its role in metabolic disorders and treatments such as semaglutide.
For now, the Stanford team wants to trace the developmental origins of the spinal cord and understand how diseases such as SMA and ALS damage hindbrain neurons. The cells that eventually become parts of the human brain appear to make fundamentally different choices before there is anything recognisable as a brain. By the time the brain looks like one organ, its cells may already be carrying the history of two very different beginnings.










Space & Physics
Can Studying Cancer Tumours in Space Help Improve Chemotherapy on Earth?
Researchers are studying miniature models of colorectal cancer aboard the International Space Station to understand whether microgravity changes how cancer cells respond to chemotherapy.

Two people diagnosed with the same type of cancer may not respond to the same treatment in the same way. A chemotherapy drug that works well for one patient may be less effective for another. This happens partly because tumours differ in their genetic makeup, growth patterns and response to medicines. Understanding these differences is vital for developing cancer research and treatments that work better for individual patients.
By sending miniature models of cancer tumours into space, scientists at Wake Forest Institute for Regenerative Medicines in the United States are exploring an unusual way to explore the problem. They are investigating whether the absence of normal gravity changes how colorectal cancer cells respond to chemotherapy. The project, called Tumor Avatars in Space (TAVIS), uses the International Space Station (ISS) as a laboratory to study how cancer cells behave in microgravity.
The experiment uses organoids, which are small, three-dimensional models of human tissues grown in laboratories. For this project, researchers developed tumour organoids using cancer cells collected from patients with colorectal cancer. These miniature models retain some of the biological features of the original tumours, allowing scientists to study how they respond to medicines.
The researchers will compare how these tumour models respond to chemotherapy in space and on Earth. By studying the differences, they hope to understand whether microgravity changes the way cancer cells react to treatment.
Why Study Cancer Cells in Space?
Gravity influences how cells grow and arrange themselves. On Earth, cells are affected by gravitational forces and the way they settle within their surroundings. In microgravity, these conditions change, allowing cells to form three-dimensional structures in different ways. This makes space an interesting environment for studying how cells behave. Researchers want to know whether changes in these conditions can affect tumour growth, cell activity and responses to cancer drugs.
Cancer tumours are made up of more than just cancer cells. They contain different types of cells that interact with one another and their surroundings. These interactions can influence how a tumour grows and responds to treatment. Studying three-dimensional tumour models can help scientists understand some of these processes better.
In the TAVIS experiment, researchers will examine whether colorectal cancer cells become more sensitive to chemotherapy under microgravity conditions. If they find differences, they will investigate the genetic and cellular changes responsible for them. One area of interest is how cancer cells use energy. This process, known as metabolism, helps cells grow, survive and carry out their functions. Changes in metabolism could influence how effectively chemotherapy destroys cancer cells.
The researchers hope to identify the biological processes behind any changes in treatment response. They will then investigate whether similar effects can be reproduced on Earth, potentially by targeting particular genes or cellular processes.
What are Tumour Organoids?
Organoids are miniature, three-dimensional structures grown in laboratories using stem cells or cells taken from human tissues. Depending on the cells used, scientists can grow models that reproduce certain features of organs such as the intestine, liver, brain and lungs. In cancer research, scientists can use cells collected from a patient’s tumour to grow patient-derived tumour organoids. These models retain some of the characteristics of the original cancer and allow researchers to test how different medicines affect it.
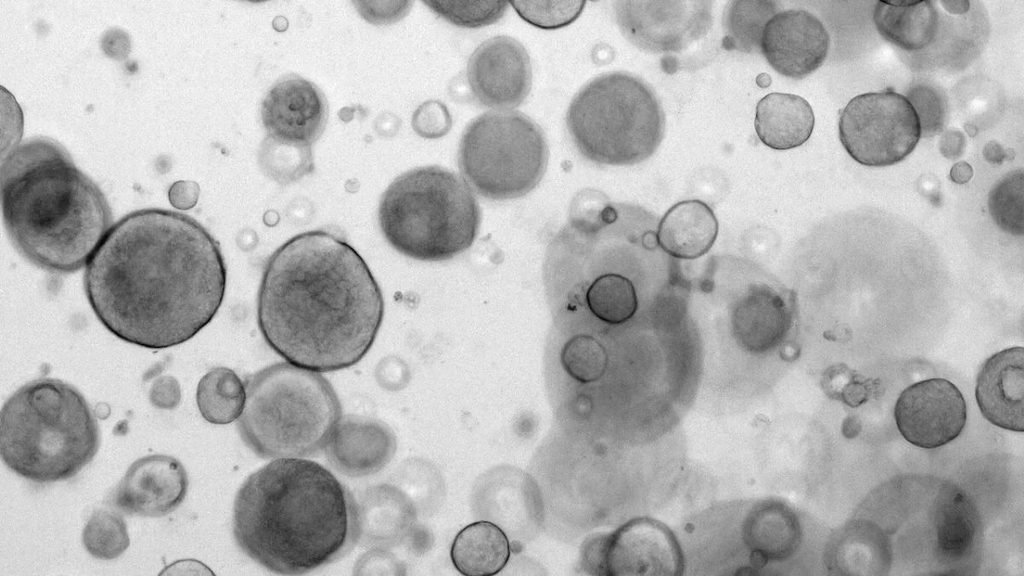
This approach provides more information than experiments using cancer cells grown in a flat layer in laboratory dishes. Since organoids have a three-dimensional structure, they can better represent some of the conditions in which cells grow and interact inside the body.
Researchers are also studying whether patient-derived organoids could help doctors identify treatments that are more likely to work for individual patients. However, this approach still requires further research and is not yet a replacement for established clinical treatment decisions.
Can it Help Cancer Treatment?
The TAVIS project is part of a wider effort to use space-based research to understand human biology and develop medical applications on Earth. After the experiment, researchers will compare the space-grown tumour models with those maintained on Earth. They will examine whether microgravity caused changes in the cancer cells and whether those changes affected their response to chemotherapy.
“If microgravity makes these tumors more responsive, we can look for the genetic changes behind that and try to induce the same changes here on Earth,” said Shay Soker, Ph.D., WFIRM professor and principal investigator of the study. “It’s similar in spirit to immunotherapy, which makes tumors more visible to the immune system. The tumor can run, but it can’t hide.”
If the space-grown models respond differently, scientists will investigate whether the same effects can be produced under normal conditions on Earth. This could help identify new ways to make cancer cells more responsive to existing treatments.
The experiment does not mean that cancer can be treated more effectively in space. Instead, it uses the unusual conditions aboard the ISS to investigate biological changes that are difficult to study in conventional laboratories. By understanding how cancer cells respond to different conditions, researchers hope to gain new insights into tumour behaviour, drug development and the possibility of more personalised cancer treatment.
Health
Over 1,000 Cancer Drug Formulations Become Cheaper Across India
India has reduced prices across 1,031 anti-cancer medicine formulations, with the government estimating annual consumer savings of 3,502 crore rupees.

Cancer treatment can involve months or even years of medication, repeated diagnostic tests, hospital visits and specialised procedures. For many Indian families, the financial strain continues long after the initial diagnosis. Against this backdrop, a government intervention to reduce the prices of more than 1,000 anti-cancer drug formulations has come into effect on November 9. The National Pharmaceutical Pricing Authority (NPPA), under the Department of Pharmaceuticals, has rationalised trade margins on 137 identified non-scheduled anti-cancer drugs. The government estimates that the revised prices will save consumers 3,502.31 crore rupees annually.
According to the Ministry of Chemicals and Fertilizers, 76 pharmaceutical companies have reported revised maximum retail prices (MRPs) for 1,225 formulations covering 121 drugs. Of these, 1,031 formulations have registered price reductions. Around 600 brands have reported reductions exceeding 50%, while the highest reduction stands at 96.45%.
The intervention is significant given the scale of cancer in India. The Indian Council of Medical Research’s National Cancer Registry Programme estimated 15.69 lakh new cancer cases in 2025. Breast, lung and mouth cancers featured among the leading cancer sites.
What has Changed in Medicine Pricing?
The latest intervention focuses on non-scheduled medicines, which are not subject to the same ceiling-price mechanism as drugs included in the National List of Essential Medicines.
The Drugs (Prices Control) Order, 2013, gives the government the power to control medicine prices when necessary to protect public interest. It fixes maximum prices for scheduled medicines, while prices of non-scheduled medicines are generally monitored. Using this order, the government has now stepped in to limit the trade margins on the selected anti-cancer medicines.
Trade margins represent the difference between the price at which medicines are supplied through the distribution chain and the price at which they are sold to consumers. Excessive mark-ups can make medicines significantly more expensive before they reach patients. Under the new arrangement, the trade margin on the identified medicines has been capped at 30% of the MRP. The measure follows a similar exercise in 2019, when trade margins on 42 non-scheduled anti-cancer medicines were rationalised.
The revised prices cover medicines used in treating different cancers. These include Bevacizumab, used for lung, colon, ovarian and cervical cancers; Denosumab, used in breast and prostate cancer patients to prevent bone loss; and Pegfilgrastim, prescribed to prevent neutropenia in cancer patients.
The price changes are substantial for several brands. Zydus Lifesciences’ Bevacizumab brand Bryxta, for instance, has seen its MRP fall from 25,995 rupees to 3,318 rupees. Reliance Life Sciences’ Abiraterone acetate brand Abirone has declined from 41,250 rupees to 3,218 rupees. Similarly, the price of Reliance Life Sciences’ Peg-ReliGrast has fallen from 5,331 rupees to 1,258 rupees.
Cancer Drugs: Financial Burden of Cancer Care
The importance of reducing medicine prices becomes clearer when viewed against the financial burden of cancer treatment. A study published in Frontiers in Public Health in 2023, involving 12,148 cancer patients across seven treatment centres in India, estimated the average annual direct out-of-pocket expenditure on cancer treatment at 3.31 lakh rupees per patient. Medicines accounted for 45% of expenditure during hospitalisation, while diagnostics contributed 36.4% of outpatient treatment expenditure.

The findings illustrate why medicine affordability matters, particularly for patients who require repeated treatment. Even when the cost of a particular drug declines, expenses related to diagnostics, surgery, hospitalisation and travel can continue to weigh heavily on households.
What Happens Next?
The revised prices will apply to the identified medicines, including 10–15 drugs that have not yet been launched in India. Their prices will also be subject to the margin restrictions when they enter the market. Manufacturers can undertake annual price increases in accordance with the Drugs (Prices Control) Order, 2013, subject to continued compliance with the maximum permissible trade margin.
The NPPA has also directed retailers, dealers, hospitals and medical institutions to prominently display the revised MRP lists. State Drug Controllers will monitor compliance. Consumers can verify medicine prices through the Pharma Sahi Daam mobile application and the NPPA website. The reduction addresses an important component of cancer treatment expenditure: the price patients pay for medicines. Its impact, however, will depend on whether the revised prices are implemented consistently across pharmacies and hospitals, and whether patients can access the medicines they need.
Lower medicine prices can ease a substantial part of the financial burden. Making cancer treatment affordable, however, will also require attention to diagnostic costs, hospital charges and access to quality treatment across the public healthcare system.
Health
How Rubella Virus Finds Its Way Into the Placenta: Scientists Identify a Human Cell Receptor
A new Nature study identifies Nectin-4 as a receptor that helps the rubella virus enter placental and respiratory cells, offering insight into congenital rubella syndrome.
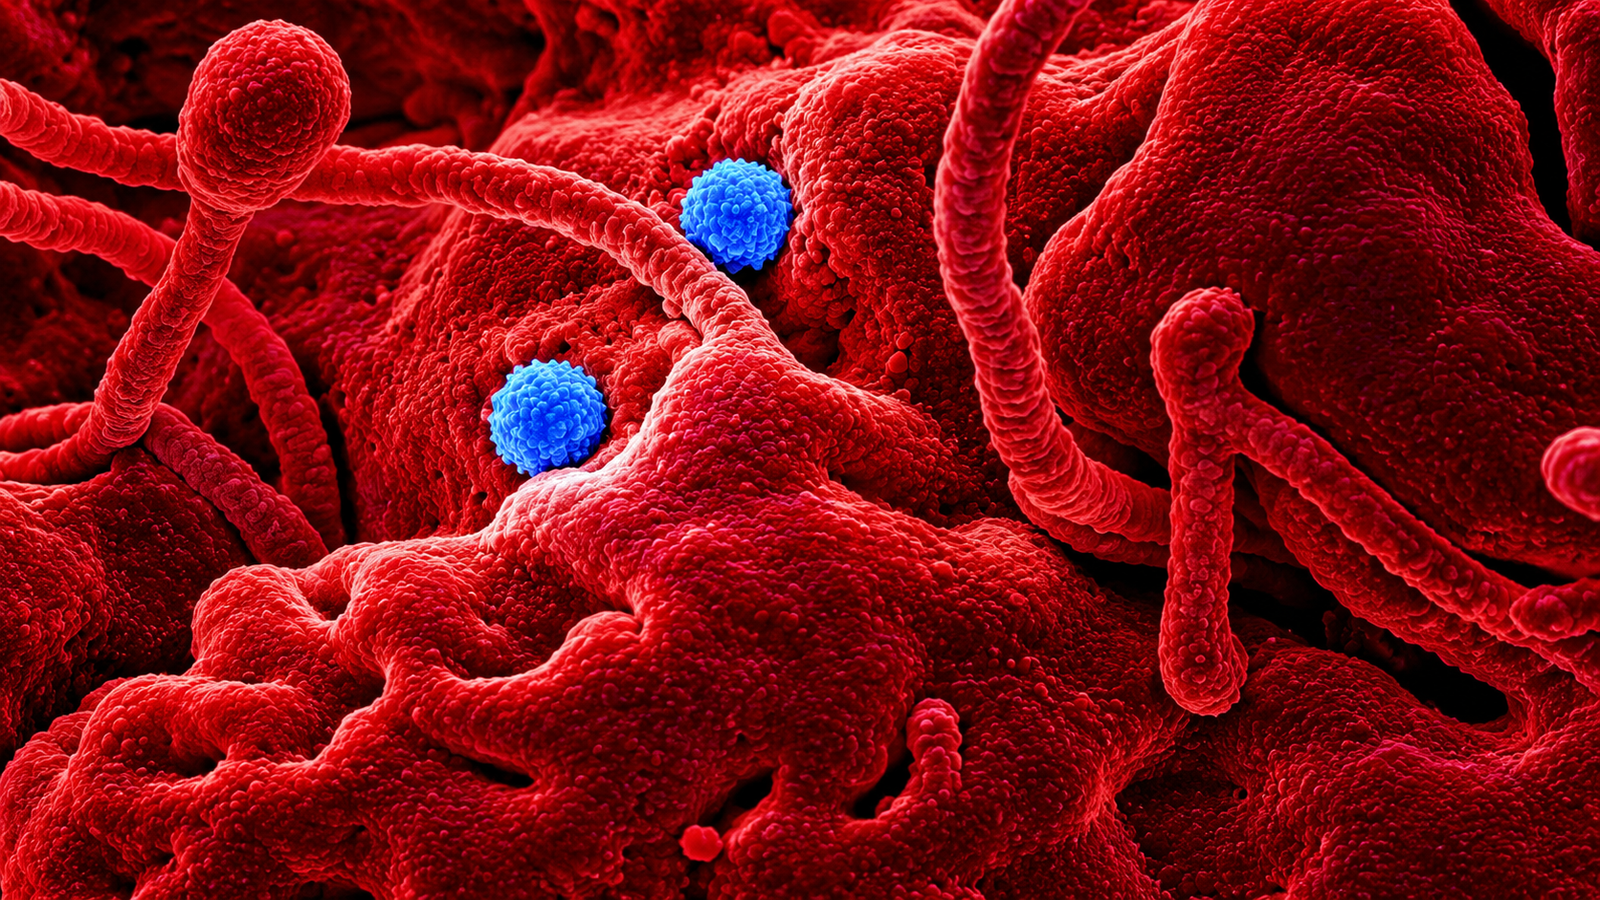
An infection that causes little more than a rash and mild fever in many people can have devastating consequences when it occurs during pregnancy. Rubella, a contagious viral disease, can cross the maternal–foetal interface and interfere with the development of an unborn child, causing hearing loss, heart defects, cataracts and other complications collectively known as congenital rubella syndrome (CRS).
An estimated 26,859 children were born with congenital rubella syndrome worldwide in 2024, according to a modelling analysis published by the US Centers for Disease Control and Prevention (CDC) in July 2026. Although this represents a substantial decline from an estimated 101,381 cases in 2012, the disease continues to affect newborns in countries where vaccination coverage remains inadequate. But how does the rubella virus enter the cells lining the respiratory tract and the placenta?
A study published in Nature identifies a protein called Nectin-4 as one of the cellular entry points used by the virus. The finding offers a closer look at how rubella establishes infection in two tissues central to its transmission and its effects during pregnancy.
Protein That Opens the Door
Like other viruses, rubella cannot reproduce on its own. It must enter a living cell and use its machinery to produce new viral particles. This often begins when proteins on the virus’s outer envelope bind to specific molecules on the surface of a human cell. These molecules, called receptors, determine which cells a virus can enter. Identifying them helps researchers understand why certain tissues are vulnerable to infection.
The research team found that rubella uses Nectin-4, a cell-adhesion protein, to gain entry into respiratory and placental cells. Nectin-4 normally helps neighbouring cells maintain contact with one another and is present in several human tissues. The virus carries two envelope proteins, E1 and E2, which participate in its interaction with host cells. The researchers found that this viral protein complex interacts directly with Nectin-4. Once the proteins bind, the cell draws the virus inside through a process called receptor-mediated endocytosis, in which a section of the cell membrane folds around an external particle.
To establish the receptor’s role, the team combined protein-interaction analysis with CRISPR-Cas9 screening. They found that cells that were initially resistant to rubella infection became susceptible after Nectin-4 was introduced. Removing or blocking the protein, meanwhile, reduced infection. This offered evidence that Nectin-4 is involved in the virus’s entry into human cells, rather than simply being present alongside the infection.
What Happens at the Maternal–foetal Interface?
The finding has particular relevance to the placenta, the organ through which oxygen and nutrients pass from the mother to the developing foetus. During pregnancy, rubella can infect placental tissue and subsequently reach the foetus. The risk of serious complications is highest during early pregnancy, when the organs are developing. An infection during this period can result in miscarriage, stillbirth or congenital abnormalities.
The researchers examined syncytiotrophoblasts, specialised cells that form the outermost layer of the placenta and come into direct contact with maternal blood. These cells constitute an important part of the barrier between maternal circulation and the developing foetus.
Their experiments showed that Nectin-4 is abundantly expressed in these cells and facilitates rubella infection. When the researchers blocked the receptor, infection in laboratory models of placental tissue declined. The result helps explain how the virus can establish an infection at the maternal–foetal interface. It also identifies a specific cellular interaction that researchers can investigate when studying the transmission of rubella during pregnancy.
There is, however, an important limitation. The team found that rubella could also infect other placental cell populations through pathways that do not depend on Nectin-4. Blocking this single receptor may therefore be insufficient to prevent the virus from infecting the entire placenta.
A Shared Entry Route With Measles
The research also sheds light on rubella infection in the respiratory tract, where the virus initially establishes itself after entering the body. Using laboratory models of human airway tissue, the researchers found that Nectin-4 facilitates viral entry through the basolateral surface of respiratory epithelial cells, which faces the underlying tissue. After entering and replicating within these cells, newly produced viral particles are released from the opposite, airway-facing surface.
This arrangement offers a possible explanation for how rubella infects respiratory tissue and releases viral particles into the airways. Nectin-4 is also recognised as a cellular receptor for the measles virus. The finding that both viruses use the same human protein is an interesting connection, although the two infections involve different molecular interactions and should not be assumed to follow identical pathways.
Could Blocking the Receptor Prevent Infection?
The discovery raises the possibility of developing antiviral treatments that interfere with the interaction between rubella and Nectin-4. A molecule capable of preventing the viral envelope proteins from binding to the receptor could potentially restrict the virus’s entry into susceptible cells. The researchers’ experiments, in which blocking Nectin-4 reduced infection, offer an initial basis for investigating this approach.
For congenital rubella syndrome, the potential application is particularly relevant. Preventing the virus from establishing an infection in placental tissue could eventually help researchers explore ways of reducing the risk of foetal infection.
Such an application remains a research possibility, however. The experiments were conducted using laboratory cell and tissue models; they do not establish that receptor-blocking treatments can prevent congenital rubella syndrome in pregnant women. The alternative routes of placental infection identified by the researchers also present a challenge for any treatment targeting Nectin-4 alone.
Vaccination Remains Central to Prevention
The findings come at a time when rubella vaccination has substantially reduced the global burden of infection, although elimination remains uneven across countries. The CDC recorded 31,593 reported rubella cases worldwide in 2024. This figure reflects infections detected and reported through national surveillance systems, rather than the full number of people infected. The WHO, meanwhile, estimates that around 100,000 infants are born with congenital rubella syndrome annually, using a broader global estimate. These figures come from different reporting and estimation approaches and should not be treated as directly comparable.
By 2024, 179 of 194 countries had introduced rubella-containing vaccines into their routine immunisation programmes, according to the CDC. Global coverage with the first dose rose from 39% in 2012 to 73% in 2024. India includes measles-rubella vaccination in its Universal Immunisation Programme, with two routine doses recommended during childhood. Sustaining coverage is important because rubella infection in an unvaccinated pregnant woman can have consequences that extend well beyond the period of the initial illness.
For now, the identification of Nectin-4 does not change how rubella is prevented or treated. Its importance lies in revealing a previously insufficiently understood interaction between the virus and human cells. Researchers now have a specific receptor to investigate as they work towards understanding how rubella reaches placental tissue and whether that process can eventually be interrupted.

Global Climate Finance Hits Record $1.9 Trillion, but Vulnerable Nations Continue to Face Adaptation Funding Gap

India Ranks 28th in Global Climate Ranking, Down Five Places

Global fossil fuel emissions projected to fall in 2026, but India’s emissions to rise 4.4%

NASA recruits new astronauts for future Moon Base and Mars missions

Between Lectures and Lyrics: Kabeer Is Building a Malayalam Hip-Hop Career One Self-Taught Skill at a Time

Indian universities lead Asia in research output per faculty, but the country’s top six all slip in QS ranking

Europe Braces for Extremes as Commission Unveils Climate Resilience Framework

Delhi’s Air Quality Paradox: Lower Average, Higher Everyday Pollution

NMC Directs Medical Colleges to Set Up Patient Safety Committees

Brazil’s Amazon deforestation hits record low. Can the recovery last?
-

 Math4 months ago
The 2026 Fields Medals: Four Proofs, Four Decades-Old Problems Solved
-
EP Deep Dive: Data & Solutions4 months ago
After Kerala’s Deadliest Landslide, the Hardest Thing to Rebuild Was Childhood
-
EP Deep Dive: Data & Solutions4 months ago
West Asia Crisis: Can Kerala’s Returning Gulf Migrants Find a Future in the Green Economy?
-
Space & Physics6 months ago
India Semiconductor Mission: ‘It’s Not About Fabs. It’s About Building An Entire Ecosystem’
-
Interviews2 months ago
From Scams to Screens: How the National Stock Exchange Rewrote India’s Equity Story
-
Climate & Environment5 months ago
The Climate World Cup? How Climate Change Could Affect Player Performance at the 2026 World Cup
-
Society4 months ago
What Is Civilisational Diplomacy? Understanding India’s Newest Foreign Policy Tool
-
Society5 months ago
From Bell Labs to the Classroom: A Second Career in Teaching















