
Connect with us

Health

Air Pollution Claimed 1.7 Million Indian Lives and 9.5% of GDP, Finds The Lancet

In 2022 alone, fine particulate pollution — PM2.5 — killed an estimated 1.7 million people in India, according to the Lancet Countdown on Health and Climate Change 2025.


Joe Jacob

Published

on

airpollution jpeg
Image credit: Yigit Karaalioglu/Pexels

In 2022 alone, fine particulate pollution — PM2.5 — killed an estimated 1.7 million people in India, according to the Lancet Countdown on Health and Climate Change 2025.

The same toxic particles that fill Delhi’s winter air and blanket cities from Kanpur to Kolkata also caused economic losses equivalent to 9.5% of India’s GDP, revealing that air pollution is not just a public health emergency, but a national economic crisis hiding in plain sight.

A Crisis Woven into Everyday Life

India’s worsening air quality is no longer a seasonal problem. According to The Lancet Countdown, over a third of Indians were exposed to PM2.5 levels exceeding World Health Organization (WHO) limits for more than 10 months of the year.

Rising temperatures, urban sprawl, and fossil fuel combustion — from coal-fired power plants to vehicle emissions — have created a deadly feedback loop that is choking the country’s lungs and its economy.

“Air pollution in India is a silent pandemic. It’s not only shortening lives, but undermining productivity, healthcare systems, and economic growth,” said Dr. Marina Romanello, Executive Director of The Lancet Countdown, in the report’s global launch statement.

The Health Toll: From Newborns to the Elderly

The Lancet Countdown 2025 estimates that the global death toll from air pollution reached 8.3 million in 2022, with India accounting for over one-fifth of those fatalities.

PM2.5 — particles less than 2.5 microns in diameter — penetrate deep into lungs and bloodstreams, causing or worsening heart disease, stroke, diabetes, and respiratory illness.

In India, the burden falls disproportionately on the poorest households, who are more likely to live near highways, coal plants, or industrial clusters and have limited access to healthcare.

Children and elderly people are the most vulnerable: the report highlights that exposure to dirty air increases the risk of low birth weight, premature births, and chronic illness later in life.

Counting the Cost: 9.5% of GDP Lost

The Lancet Countdown’s economic assessment, based on lost labour productivity, healthcare costs, and premature deaths, found that India lost 9.5% of its GDP in 2022 due to air pollution-related impacts.

That’s roughly equivalent to USD 300 billion — more than India’s entire annual education and health budgets combined.

Urban centres such as Delhi, Lucknow, and Patna rank among the most polluted in the world.

Air pollution is estimated to reduce life expectancy in northern India by up to 7 years, according to the Energy Policy Institute at the University of Chicago, underscoring how pervasive the damage has become.

“For a fast-growing economy like India, this is a double blow,” said Prof. Randeep Guleria, pulmonologist and former AIIMS director. “It burdens healthcare systems while reducing worker output — exactly the opposite of what a young nation needs.”

Climate and Air: The Same Enemy

The report connects India’s pollution crisis to its dependence on fossil fuels — especially coal — which remains the largest source of both CO₂ and PM2.5 emissions.

While government programmes such as the National Clean Air Programme (NCAP) and electric mobility initiatives aim to reduce pollution, progress has been slow.

Many of the dirtiest thermal plants continue to operate without meeting emission standards, and vehicle emissions remain poorly regulated outside major cities.

“Air pollution is not a separate problem from climate change — it’s the same story told through different symptoms,” noted Dr. Romanello. “Every tonne of coal burned harms both lungs and the climate.”

This linkage is echoed in India’s own National Electricity Plan 2032, which outlines aggressive renewable targets, and in Ember’s 2025 analysis, which found that expanding coal capacity further would be economically irrational — a finding that strengthens the case for rapid decarbonisation.

Health as an Economic Argument

The Lancet Countdown reframes pollution not just as an environmental or health challenge, but as an economic imperative.

In India, labour losses due to heat and pollution exposure have grown by 42% since the early 2000s, with outdoor and informal workers suffering the most.

As heatwaves and smog increasingly overlap, lost work hours and rising healthcare costs could slow GDP growth by up to 1.8 percentage points annually by the mid-2030s if left unchecked.

Experts say cleaner power and transport sectors could deliver rapid wins:

  • Phasing out coal and shifting to renewables can cut PM2.5 emissions by over 60% in key industrial zones.
  • Expanding public transit and EV adoption can reduce vehicular PM2.5 by one-third in metropolitan regions.
  • Strengthening NCAP’s monitoring and enforcement could save hundreds of thousands of lives each year.

From Policy to Breathable Air

Despite India’s national clean air mission and renewable push, enforcement and coordination remain major gaps.

The report calls for integrating air quality and climate policies, arguing that cutting fossil fuel use provides a “double dividend” — cleaner air and fewer greenhouse gases.

This integration has begun in limited form: several Indian states, including Gujarat and Maharashtra, have introduced emissions trading schemes for industrial pollutants.

But experts say scaling such initiatives nationally, alongside stricter vehicle standards and urban planning reforms, is critical for measurable results.

A Moment of Reckoning

The Lancet Countdown 2025 warns that air pollution and climate impacts are already reversing health gains made over decades.

India’s choice is no longer between growth and clean air — it’s about whether growth can continue at all under the weight of rising illness, lost labour, and degraded ecosystems.

“Air pollution is robbing India of its demographic dividend,” the report concludes. “Clean air is not a luxury; it’s a prerequisite for sustainable development.”

As the smog season begins once again in northern India, the data are unambiguous:

The invisible killer is now visible — and unaffordable.

References:

The Lancet Countdown on Health and Climate Change 2025; The Lancet; Energy Policy Institute at the University of Chicago (EPIC); Ember; CREA.

Health

Not Broken but Unheld: A New UN Report Asks Us to Tend the Forest, Not Only the Tree

A new UN report on youth mental health calls for an ecosystem approach linking well-being with education, work, housing, climate, technology and community.

Prof Narnia Bohler-Muller

Published

on

When Youth Mental Health Becomes a Housing, Work and Education Question
Image credit: Timur Shakerzianov/UnSplash

A new UN report asks us to rethink youth mental health not simply as a matter of individual symptoms, but as a question of the wider ecosystems in which young people live, learn and work.

There is a sentence in the middle of the United Nations’ new report on youth mental health that I have not been able to set down: “There is no ‘cure’ for being human”. Thriving, its authors write, does not mean the absence of hardship. It is a rare admission for an institution whose native idiom is targets and indicators, and it signals something larger than a change of tone.

Youth Mental Health & Well-being in an Uncertain World: A Global Call to Action, produced by the UN Youth Office and the United Nations University International Institute for Global Health and launched in September’s UN General Assembly, asks governments to stop treating young people’s distress mainly as a matter of individual symptoms. Instead it proposes an ecosystem model of 10 linked domains: governance, education, decent work, housing, climate, digital technology, peace, the arts, sport and spirituality. Each can tend or erode a young person’s life.

Youth Mental Health: The Sobering Global Figures

The figures are sobering. One in seven people aged 10 to 19 lives with a mental health condition, and half of these conditions emerge by 18. Suicide remains among the leading causes of death for the young, and close to three-quarters of the world’s suicides occur in low- and middle-income countries. Yet only 56% of countries have a child and adolescent mental health policy, against 81% with adult policies, and most spend less than 2% of their health budgets on mental health.

More telling than the numbers is the report’s philosophical turn. Drawing on Tyler VanderWeele’s flourishing research at Harvard, it insists that well-being belongs to the person and to her world at once: the tree and the forest must both be doing well. It speaks of relational well-being, of care, connection and community as the ground of collective health, and of each young person as, in some measure, the embodiment of her surroundings.

Flourishing Denied

African readers will recognise this terrain. Umuntu ngumuntu ngabantu; motho ke motho ka batho: a person is a person through other persons. Ubuntu has long held that personhood is not a possession but an achievement of relation, and that no self can flourish in a community that is failing. The report arrives, by way of Harvard, at a truth spoken in isiZulu, isiXhosa and Sesotho for generations. I welcome that convergence, and want to push it further.

In my own work I call this condition flourishing denied: the tearing of the relational webs that hold a life, from the household to the planet. Read this way, much of what we name youth mental illness is not, or not only, a malfunction inside the young person. It is an accurate registration of a world that has come apart around her. The report comes close to saying so. Citing UNICEF, it notes that six in 10 young people faced systemic challenges in the past year, led by economic instability and climate change, and that more than half lack hope for the future. UNESCO, it adds, has found an erosion of young people’s belief in their own futures, rooted in historical injustice. Despair of this kind is not a disorder of perception. It is, very often, perception itself.

This matters because the language of resilience, which the report uses generously, can return the burden to the young. We teach adolescents to regulate their emotions, to breathe, to cope, and then send them out into economies that have no place for them. Resilience is a virtue; it is not a policy. No young person should have to become heroically adaptable to survive conditions a decent society would not impose.

Nowhere is this clearer than at home. In the second quarter of this year Statistics South Africa reported youth unemployment of 47.4% among 15- to 34-year-olds, and more than a third of 15- to 24-year-olds were neither employed nor in education or training. The report cites South African research finding that between 21 and 24.5% of students live with conditions ranging from social anxiety to post-traumatic stress. Set side by side, these figures make the ecosystem model concrete. For many young South Africans, decent work is not one domain among 10; it is the load-bearing wall.

Hope In Its Pages

The report’s most consequential move is to anchor all this in human rights. It recalls the Secretary-General’s insistence that mental health is a right, not a privilege, and General Assembly resolution A/RES/77/300, which defines mental health not by the absence of a condition but by an environment in which dignity is respected. South Africa needs no persuading. Our Constitution guarantees access to health care, adequate housing and a basic education, and an environment not harmful to health or well-being. The report offers a way to read these guarantees together: a student’s panic attack in an overcrowded residence may be a housing question, a safety question and a labour-market question.

There is hope in its pages too. Much of the report’s texture comes from youth-led initiatives, many of them African: peer-support circles, restorative justice networks, arts-based healing, digital helplines. Young people are already building the ecosystems that states have been slow to fund, and the report rightly insists that they be co-authors of the response, not its beneficiaries.

A call to action is only as good as the action it calls forth, and the report is candid that policies on paper have not yet become services on the ground. Its model is a map. What South Africa needs now is the political will to walk it: to budget for mental health, to design labour, housing and education policy with young minds in view, and to resource the young people already doing the work.

There is an isiZulu word I return to often: ngisazophumelela, I will yet succeed; I am still becoming. It is not a statement of certainty but a grammar of persistence, a future tense spoken from inside difficulty. The question the UN has put to us is whether we will build a world in which it can come true.

Disclaimer: Prof Bohler-Muller writes in her personal capacity and does not necessarily represent the views or position of the University of the Free State. 

Continue Reading

Health

Ebola Outbreak Worsens in DRC as WHO Calls for Urgent Patient Care

More than 8,000 cases have been reported in the Democratic Republic of the Congo, while limited access to treatment and ongoing violence are complicating efforts to contain the outbreak.


Published

on

Healthcare worker administers an Ebola vaccine injection to a person as photographers document the vaccination.
WHO A research vaccination programme has been launched in Ituri, in the Democratic Republic of Congo, for health workers and other frontline personnel at increased risk of Ebola exposure. Source: UN

The Democratic Republic of the Congo (DRC) is facing its largest-ever Ebola outbreak, with more than 8,000 cases reported, according to health authority data published on Monday. The World Health Organization (WHO) has called for faster access to medical care as delays in treatment continue to contribute to deaths. While transmission has begun to decline in some areas, the number of cases remains high, WHO officials said.

With 8,067 confirmed cases and 3,901 deaths, the case fatality rate is more than 48 per cent in 63 affected health zones in seven out of DRC’s 26 provinces. “While we are beginning to see a reduction in transmission in some areas, the number of cases remains high for this outbreak,” Dr Janet Diaz of the WHO Health Emergencies Programme told reporters in Geneva. WHO and its partners have expanded Ebola treatment facilities across the affected regions.

Treatment capacity has increased from only a handful of beds at the beginning of the outbreak to more than 1,600 beds across 50 treatment centres in seven affected provinces. Authorities plan to increase the capacity to more than 2,000 beds. Nearly 400 health workers have also been trained as part of the response, with a training hub established in Bunia. Health workers are particularly important in Ebola treatment because patients require specialised care and close monitoring. “Every patient bed requires a skilled workforce to provide safe, quality care around the clock,” Diaz said.

Erupting Violence Amid Health Concerns

Amid the growing Ebola crisis,Aid teams have raised concerns about the situation at Kigonze displacement camp in Bunia, in northeastern Ituri province. According to reports, soldiers entered the heath camp searching for weapons and people suspected of links to non-State armed groups. Gunshots were also reported. The violence has added another challenge to efforts to control the Ebola outbreak, as displacement can make it harder for people to access healthcare and for response teams to trace and monitor cases.

According to the UN aid coordination office, OCHA, the camp hosts nearly 19,000 displaced people. Residents have faced “armed violence, threats and intimidation against civilians, arrests, forced displacement and the destruction of shelters”, the Office said. Echoing those concerns, UN Humanitarian Coordinator in the DRC, Damien Mama, said that many families had left the site to seek refuge with host families.

Mr. Mama also stressed that the civilian character of the site must be preserved and that families “who have already lost everything” must be able to find safety and dignity where they have find refuge. The dispersal of families also raises serious public health concerns, as Kigonze is among the sites covered by the ongoing Ebola response.

In Need of an Efficient System

Oxygen is another major challenge. It is an important part of supportive treatment, particularly for patients suffering from severe Ebola disease, but remains unavailable or unreliable at many health facilities, especially in emergency settings.
DRC Ebola outbreak
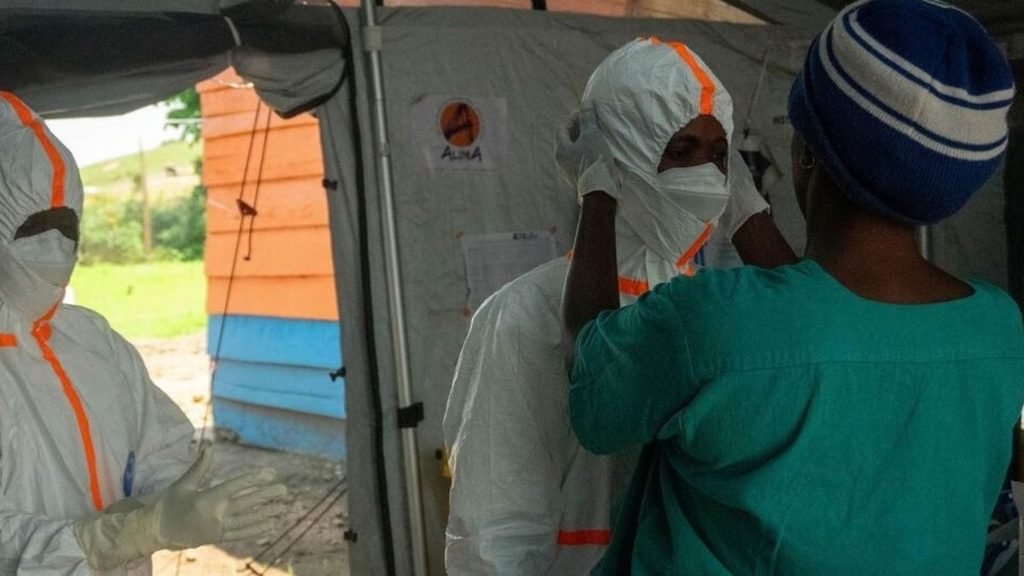
UNOCHA/Priscilla Lecomte At the Ebola treatment centre ran by the NGO ALIMA, the medical staff follows strict infection prevention and control measures to prevent the spread of Ebola. this include wearing full personal protective equipment. Source: UN

According to WHO, improving oxygen access requires more than supplying cylinders and equipment. It also depends on reliable infrastructure, trained healthcare workers and systems capable of delivering oxygen to patients when and where it is needed. There is currently no approved vaccine specifically for Ebola Bundibugyo virus, although vaccine trials are underway.

WHO has allocated 20,000 doses of the Ervebo vaccine for a research vaccination programme in Ituri province. The vaccine has previously been used against Ebola Zaire virus. WHO and its partners continue to focus on early detection, rapid referral, supportive treatment and improving access to healthcare as they work to contain the outbreak. “Delays in seeking care, together with challenges in access and referral, continue to complicate the response,” Diaz said.

Continue Reading

Health

Worms in Tuna? Why a Brazil Study Has Triggered an Indian Advisory

A Brazil study found parasites in 51 of 53 skipjack tuna, including some in muscle tissue. CMFRI says the finding should not be applied to Indian tuna.

Published

on

Fresh tuna displayed at a fish market, relevant to concerns over parasites in tuna
Tuna displayed at a fish market. A Brazil study found parasites in 51 of 53 skipjack tuna, prompting questions about seafood safety. Representational image. Image credit: Nazim Zafri/Pexels

Is tuna safe to eat? That question has gained attention after a study from Brazil found a high prevalence of parasites in skipjack tuna. The researchers found parasites in 51 of 53 fish they examined. More importantly, some of the parasites were found in the muscle tissue, the part of the fish that people eat. The finding raised a food-safety concern. Some fish parasites, including Anisakis, can infect humans when contaminated seafood is eaten raw or inadequately cooked. This makes the presence of parasites in edible fish tissue more than a biological curiosity.

The concern has also reached India, where tuna is widely consumed. But the Brazilian study was conducted on fish caught in the Atlantic Ocean off Brazil. It does not tell us how common these parasites are in tuna caught in Indian waters. That distinction is now at the centre of an advisory from the ICAR-Central Marine Fisheries Research Institute (ICAR-CMFRI), Kochi.

What did the Brazil Study Find?

Researchers examined 53 skipjack tuna (Katsuwonus pelamis) caught off the Brazilian coast. Parasites were found in 51 fish, or 96% of the sample. The researchers recorded more than 1,500 parasites. They included Anisakis and parasites belonging to the Trypanorhyncha group.

The finding that drew the most attention was their presence in muscle tissue. Parasites were detected in the muscle of 31 fish, accounting for 58.5% of the sample. This is relevant to consumers because the muscle is the part of the fish that is normally eaten.

The researchers also pointed to the importance of removing the internal organs soon after the fish is caught. Proper handling can help reduce the movement of parasites from the viscera into the muscle.

Why did this Raise Questions in India?

The concern is easy to understand. If parasites can occur in the flesh of skipjack tuna, consumers may wonder whether the same thing happens in tuna sold in India. Parasite prevalence can differ between geographical regions. It can also depend on local ecological conditions and the availability of intermediate or secondary hosts such as copepods, according to CMFRI.

Skipjack tuna displayed on a white surface
A skipjack tuna, the species examined in the Brazil study that reported a high prevalence of parasites. source: CMFRI

The study therefore does not establish that Indian tuna has the same parasite prevalence as the Brazilian sample.

What does CMFRI Say?

CMFRI has advised consumers not to avoid tuna or other commercially available fish simply because parasites have been reported in fish from a particular region. The institute says fish examined along the Indian coast, including tuna, have not shown external manifestations of harmful parasitic infestation.

CMFRI also says its scientists regularly examine fish, including skipjack tuna, for abnormalities and parasites. “Scientists at CMFRI regularly examine fish, including skipjack tuna, as part of fish biology studies and observe fish for abnormalities and parasites whenever necessary. The fish examined do not show external manifestations of harmful parasitic infestation,” said Dr Grinson George, Director, ICAR-CMFRI.

What Should Consumers Do?

CMFRI recommends proper handling and cleaning of fish. Prompt removal of the intestines and other viscera is important during processing. Thorough cooking provides another layer of protection. CMFRI says proper cooking kills parasites and significantly reduces the associated food-safety risk.

The concern is greater with raw or lightly cooked seafood. In such cases, the parasite burden of the particular fish and how it has been processed become important factors.

For Indian consumers, the Brazilian study is not evidence that Indian tuna is unsafe. The more immediate lesson is about food handling. Clean fish properly, remove the viscera promptly and cook it thoroughly. There is no need to avoid tuna solely because parasites were reported in fish from Brazil.

Continue Reading

Trending













