
Society
The Ten-Rupee Doctor Who Sparked a Health Revolution in Kerala’s Tribal Highlands
Dr. V. Narayanan’s Swami Vivekananda Medical Mission Hospital in Agali — known locally as the 10-rupee hospital — stands as one of the most remarkable community health transformations in modern Kerala


Swami Vivekananda — arguably India’s most influential modern monk and one of the world’s most celebrated humanist thinkers — once said, “They alone live who live for others.” In the remote Adivasi (tribal) hamlets of Attappadi, deep in the hills of Kerala, that line is not philosophy. It is the force that quietly reshaped an entire community’s destiny.
Two decades ago, a young doctor arrived in this valley armed with nothing more than Vivekananda’s teachings and an unusual certainty: that his life’s purpose lay not in hospitals with polished floors or specialised units, but in the neglected tribal belts where even an ambulance was a distant dream. In a medical world chasing high salaries and urban careers, he walked away from all of it. Today, they call him simply: “The Ten-Rupee Doctor.”
Dr. V. Narayanan’s Swami Vivekananda Medical Mission Hospital in Agali — known locally as the 10-rupee hospital — stands as one of the most remarkable community health transformations in modern Kerala. For thousands of tribal families who once had no healthcare, the hospital is not merely a building. It is dignity restored.
The road to Attappadi coils through steep cliffs and dense forests, revealing slivers of green and shadows of mountains that appear to move with each turn. For years, headlines from this tribal hotspot in Kerala’s Palakkad district were heartbreakingly similar: child malnutrition, maternal deaths, anaemia, and a healthcare system fractured beyond recognition.
We were travelling from Kochi not to revisit that trauma, but to meet the man whose quiet, steady efforts helped change it.
When Dr. V. Narayanan arrived in 2002, Attappadi’s healthcare landscape was desolate. A few primary health centres existed in name, but medicines were scarce, staff irregular, transport unreliable, and trust nearly non-existent. Many Adivasi (tribal) families walked hours for simple ailments. Women delivering babies often did so without skilled care.
“In those early days,” he recalls, “you wouldn’t even see a bike on the road. Healthcare wasn’t inadequate — it was absent.”
But absence was precisely what he had come to confront.

How Vivekananda Became a Field Manual
The roots of his journey stretch back to his teenage years. “I was in Class 12,” he says. “It’s an age when you question everything. I began reading Vivekananda deeply. His call to serve the poor, to work in backward areas — that stayed with me.”
Medicine wasn’t his ambition. Rural development was. But his family persuaded him to study MBBS, believing it would broaden his capacity for service. It did — but only because he refused to choose the conventional path.
After completing a postgraduate programme in child health, he didn’t apply for a job. He headed straight to Attappadi — without doubts, without second thoughts. “This wasn’t a career decision,” he says. “It was a life decision.”
His first “clinic” was a mobile medical unit borrowed from the Vivekananda Medical Mission in Wayanad. Every evening he visited a different hamlet, listening to people speak about water scarcity, hunger, infections, unemployment, fear, distrust — and neglect that had accumulated over generations.
Slowly, he became a familiar figure in the valley. Mothers insisted he be the first to hold their new-borns. Elders began greeting him as one of their own.
A belonging was forming — one that medicine alone cannot create.
The Birth of the Ten-Rupee Hospital
In 2003, as patients multiplied beyond what the mobile clinic could handle, he opened a small outpatient centre in Agali. By 2006, after raising 22 lakh rupees from well-wishers and small donors, the Swami Vivekananda Medical Mission Hospital opened its doors with 10 beds, two consulting rooms, and a lab.
Its defining principle was radical: Adivasi patients would be charged only ten rupees. Always.
Administrators warned him it was economically unviable. But the doctor had seen families pushed into debt by even minor medical expenses.
“The hospital must belong to them,” he says. “Cost should never decide who lives and who dies.”
People came. Trust deepened. And trust became infrastructure.

A patient visited in the hospital says, “Here, we feel like human beings. Not cases. Not numbers. Narayanan doctor listens to us like we are his family. That is why we come.”
Another woman added softly: “When we step inside this hospital, we feel safe. There is no fear here.”
For communities long accustomed to humiliation and exploitation in medical spaces, this emotional safety mattered as much as treatment.
A Global Gap Mirrored in a Valley
Attappadi’s early struggles are not isolated. Across India, Adivasi (tribal) communities face some of the poorest health indicators — high maternal mortality, anaemia, malnutrition, tuberculosis, and limited access to skilled care.
Globally, too, Indigenous communities — from the Māori of New Zealand to Native American nations and Aboriginal groups in Australia — experience higher infant and maternal mortality, limited access to hospitals, distrust due to historic exclusion, lower life expectancy, and underfunded primary care
A 2021 UN report states that Indigenous peoples worldwide are nearly twice as likely to lack basic healthcare access. What was happening in Attappadi was part of a wider pattern — the world’s margins suffering the world’s worst health outcomes.
Dr. Narayanan stepped directly into that gap.

Healing Required More Than Hospitals
Over time, he realised medical treatment alone could not fix Attappadi’s pain.
“Pregnant women worked until delivery because they had no choice,” he says. “Many ate barely one meal a day. How can a baby survive that?”
He conducted a participatory rural appraisal across several hamlets — and what he saw changed everything. Malnutrition was linked to income instability. Illnesses persisted because basic hygiene wasn’t possible. Women were dying because poverty didn’t allow rest.
“It felt like pouring water into a pot full of holes,” he says. “We had to strengthen the pot — not just keep pouring.”
The hospital expanded into a movement that worked on, restoring nutrition, improving sanitation, supporting livelihoods, strengthening housing, reviving agriculture, education, and building self-reliance.

Village health workers — trained women and men from each hamlet — became ambassadors of preventive care. From an initial 40, tthe network has grown to nearly 130 health workers across Attappadi.
Education too became central. The Mission school today teaches 600+ children, and the valley now has young people pursuing medicine, nursing, and engineering — an unimaginable shift a decade ago.
Growing, But Never Losing Its Soul
The hospital today has 50 beds, 12 full-time doctors, and over 80 staff. Across the Mission’s programmes, more than 200 people work toward one idea: dignity. Nearly 70% of all patients remain Adivasi (tribal).
The next dream: a 100-bed hospital. Construction for new OP wings and a skill development centre has already begun.
CSR funding keeps the institution afloat, but the ten-rupee fee remains untouched.
“It will never change,” he says. “This hospital exists because of them. It must always belong to them.”
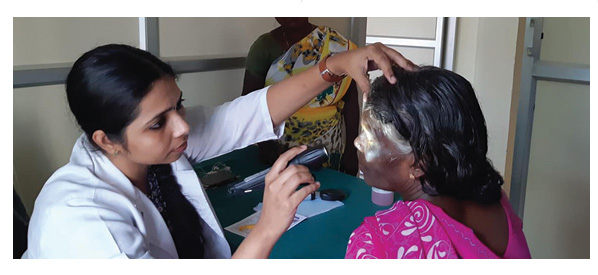
A Revolution Fuelled by Belonging
When asked what sustains him, Dr. Narayanan doesn’t speak of recognition. Instead, he points to his staff — many of whom left better-paying jobs to join the Mission.
“They believe in this work more than anything I’ve done,” he says. “I’m just one person. They are the movement.”
Two decades after he arrived here, the Ten-Rupee Doctor still walks through the corridors of his hospital with the same simplicity and calm that first won the valley’s trust.
In the world of global public health — dominated by budgets, systems, and crises — Attappadi offers a different narrative: that change is possible when a community finds a place where it is seen, heard, and treated as human.
Sometimes, revolutions don’t begin with policy. They begin with one person who refuses to turn away.












Society
Who Cares for India’s Older People?
On International Day of Older Persons, a HelpAge India study highlights gaps in healthcare, income, family care and social support facing older people in India, including added risks from climate-related hazards.


Growing older can change something as ordinary as getting medicines, visiting a doctor or managing a difficult day alone. For many older people, the question is not simply whether help exists, but whether someone is close enough and able to provide it when it is needed.
A recent HelpAge India study of 2,224 older people across 20 districts in 10 states offers a picture of the support systems on which they depend. It found that 94% of older people who needed care received it from family members. But that support is not equally available to everyone.
Thirteen percent of those surveyed lived alone, 33% were widows and 28% were aged 80 or above. Nearly half reported a long-term impairment, including mobility and vision difficulties. These circumstances matter because everyday care often depends on another person being physically present.
When Family is not Nearby
India’s older population continues to rely heavily on family for care. But migration for work is changing household arrangements. In the HelpAge study, 18% of households reported that a family member had migrated for work. Sons accounted for 76% of those migrants.
For older people living alone, neighbours often fill part of the gap. Thirty-eight percent depended on neighbours for care, while 20% relied on family members living elsewhere. Sixteen percent said they received no care.
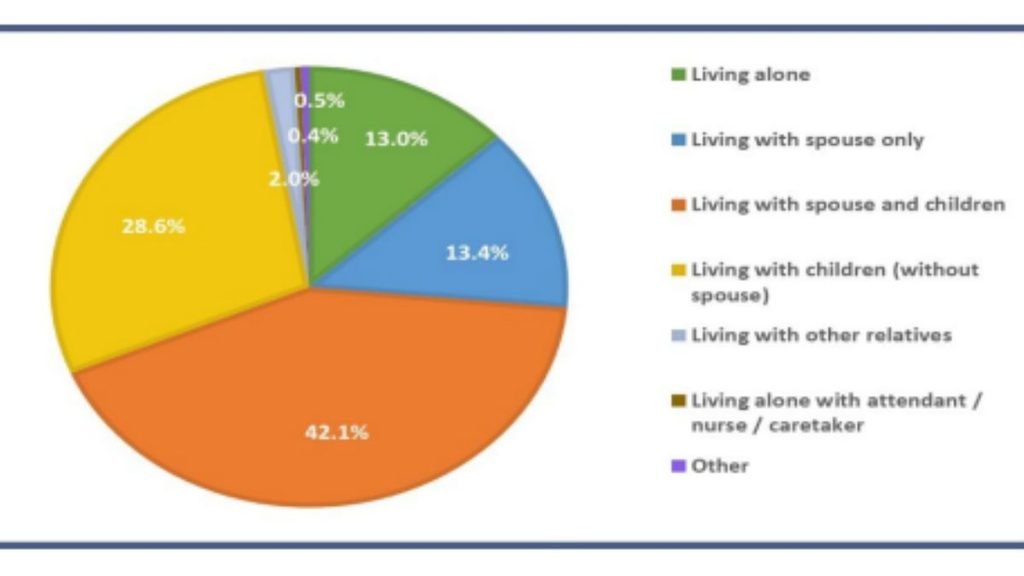
Distance does not necessarily mean that families stop supporting older relatives. Financial assistance and regular communication can continue. But some needs cannot be met remotely: taking someone to a hospital, collecting medicines, helping them move around the house or responding when they suddenly fall ill. This distinction becomes particularly important during emergencies.
Health Harder to Manage
The study found that 52% of respondents could not afford medicines. Public facilities were an important source of healthcare, with 51% using primary health centres and 49% government hospitals.
Climate-related events exposed some of these existing difficulties further. Seventy-eight percent of those surveyed had experienced at least one such hazard in the previous three years, with heatwaves the most common.
Among those who experienced heatwaves, 74% said illness increased and 44% said existing health conditions worsened. One-third reported difficulty accessing healthcare. These figures are less about the hazard itself than about what happens when an older person already managing health problems has fewer options for care.
“Older persons are among those most at risk from rising climate shocks, particularly those living alone or with impairments, yet they remain largely invisible in climate response efforts,” says Rohit Prasad, CEO, HelpAge India. “Climate impacts extend beyond physical hazards, affecting health, income, housing, care and social wellbeing.”
Prasad says age-related physical, financial and social challenges can limit older people’s ability to prepare for, withstand and recover from climate events. He calls for ageing to be integrated into climate adaptation, climate financing, elder-centric disaster risk reduction and social protection policies.
Income Constraint
Healthcare is only one part of financial insecurity in later life. Pensions were the main source of income for 49% of respondents. Sixteen percent had neither work nor income, while others continued to work in agriculture, agricultural labour or other forms of employment.
The ability to pay for medicines, travel to healthcare facilities, household repairs or basic necessities depends heavily on this income. Work also changes with age. The HelpAge study found that the proportion reporting no work or income rose from 11% among those aged 60–69 to 21% among those aged 80 and above.
For people who have spent much of their lives in informal employment, growing older can therefore mean entering a period with limited savings, little employment protection and greater healthcare needs.
The Problem of Access
Government schemes can provide important support, but knowing about a benefit does not always mean being able to obtain it. The study found relatively high awareness of the Public Distribution System, pensions, subsidised healthcare and housing schemes. Yet access was more difficult for people with poor health, those severely affected by climate hazards, people without formal education and those from lower socioeconomic groups.
Respondents also reported delays, difficulties with digital access and a lack of assistance with applications. For an older person with limited mobility, poor eyesight or little experience with digital services, even a relatively straightforward application can become difficult without help.
Ageing Needs More Than Family Care
India’s ageing population is growing, while the family structures that have traditionally provided care are changing.
UNFPA estimates that the number of Indians aged 60 and above could approach 193 million by 2030. That growth will increase the need for healthcare, financial support and forms of care that do not depend entirely on whether an older person’s children live nearby.
The answer is not to replace family care, which remains central to the lives of many older people. It is to ensure that those who do not have family nearby, cannot afford private care or need support beyond what relatives can provide are not left without alternatives.
Ageing policy therefore needs to look beyond longevity. It has to account for who provides care, who pays for healthcare, how older people access public services and what happens when the person they depend on is no longer close by. For many older Indians, these are not future questions. They are questions of everyday life.
Health
Not Broken but Unheld: A New UN Report Asks Us to Tend the Forest, Not Only the Tree
A new UN report on youth mental health calls for an ecosystem approach linking well-being with education, work, housing, climate, technology and community.

Society
Digital Detox: Why Taking a Break From Screens Matters
A digital detox can help children and adults reduce screen dependence, reconnect with nature and relationships, and create space for reflection and creativity.




Icnoic Matterhorn Almost Snow-Free as Record Heat Accelerates Swiss Glacier Loss

Who Cares for India’s Older People?

Climate Change Is Already on Your Dinner Table. Here Is How It Got There

India Records Driest Monsoon in 11 Years as Rainfall Deficit Hits 12.6%

Not Broken but Unheld: A New UN Report Asks Us to Tend the Forest, Not Only the Tree

From Scams to Screens: How the National Stock Exchange Rewrote India’s Equity Story

Aim for the Stars: Anjali Thomas’s Journey from a Small College in Kerala to the Frontiers of Medical Imaging

Anxiety Freezes Career Decisions. Curiosity Unfreezes Them

The Engineer of Tomorrow Is Already Here

India’s AI Moment Rests on More Than Code

-

 Math2 months ago
The 2026 Fields Medals: Four Proofs, Four Decades-Old Problems Solved
-
Climate2 months ago
After Kerala’s Deadliest Landslide, the Hardest Thing to Rebuild Was Childhood
-
Society3 months ago
West Asia Crisis: Can Kerala’s Returning Gulf Migrants Find a Future in the Green Economy?
-
Space & Physics4 months ago
India Semiconductor Mission: ‘It’s Not About Fabs. It’s About Building An Entire Ecosystem’
-
Interviews1 week ago
From Scams to Screens: How the National Stock Exchange Rewrote India’s Equity Story
-
Climate4 months ago
The Climate World Cup? How Climate Change Could Affect Player Performance at the 2026 World Cup
-
Society3 months ago
What Is Civilisational Diplomacy? Understanding India’s Newest Foreign Policy Tool
-
Society4 months ago
From Bell Labs to the Classroom: A Second Career in Teaching














